Resource Type: Research Briefs & Reports

Report: California: A Sugary Drink Excise Tax

The information in this report is intended to provide educational information on the cost-effectiveness of sugary drink excise taxes.

Executive Summary

Health impact of a $0.02 per ounce state excise tax on sugary drinks; 69 fewer 12 ounce sugary drinks servings per person in the first year; 198,000 cases of obesity prevent in 2030; 13,900 cases of diabetes prevented; 502,000 reduction in decayed, missing, or filled teeth over 10 years (Medi-Cal); Cost impact of a $0.02 per ounce state excise tax on sugary drinks; $46.89 health care costs saved per $1 invested; $1.79 billion saved in net costs; decrease in spending on sugary drinks per household in the first year is $142; $395.million saved in dental decay treatment costs over 10 years (Medi-Cal)In California, health disparities and inequities persist for specific subsets of the population – the reasons for this are deep-seated and multi-faceted. Sugary drink consumption is one health behavior for which disparities exist, and it has been linked to excess weight gain, obesity, and the incidence of type 2 diabetes, heart disease, and cancer. Federal, state, and local governments have considered excise taxes on sugary drinks to reduce consumption, reduce obesity and associated chronic disease, and provide a new source of government revenue.1,2,3 In California, statewide legislative measures to introduce sugary drink excise taxes have been proposed for a number of years in efforts to improve the health of Californians and reduce inequities, but none have passed.4

We modeled the implementation of a state excise tax on sugary drinks in California at a tax rate of $0.02/ounce. CHOICES cost-effectiveness analysis compared the costs and outcomes over a 10-year time horizon (2020-2030) of implementing a tax with the costs and outcomes associated with not implementing a tax.

The tax modeled is projected to be cost-saving (that is, the tax saves more in future health care costs than it costs to implement even absent the potential revenues). The tax is projected to decrease sugary drink consumption among California residents, prevent nearly 200,000 cases of obesity, and save more than 1.8 billion dollars in health care costs. People who consume sugary drinks are expected to spend less on these drinks with the tax in place. We also project that non-Latino Black/African American and Latino California residents will experience even greater health benefits than the average resident after the tax is implemented. These results are summarized below and in the complete report.


Background 

In California, health disparities and inequities persist for specific subsets of the population – the reasons for this are deep-seated and multi-faceted including systems that perpetuate the unequal distribution of power and resources along racial lines.5 Overconsumption of added sugars is common, with more than half of the United States population ages two years and older exceeding the daily recommended limit for added sugars put forth in the 2015-2020 Dietary Guidelines for Americans.6 Sugary drinks (defined as all drinks with added caloric sweeteners) are the number one source of added sugars that Americans consume.6In this report, Asian, Black/African American, White, and Other race/ethnicity groups refer to people of non-Latino ethnicity. Other includes people of Native Hawaiian and Pacific Islander, American Indian and Alaska Native, and two or more races.

According to recent estimates, 40% of California residents drink at least one serving of sugary drinks daily.7 Higher than average sugary drink consumption levels are common among Latino and Black/African American Californians.7 In 2018, the beverage industry spent $1 billion to advertise sugary drinks in television, digital platforms (internet and mobile), radio, magazines, newspapers, coupons, and outdoor venues in order to drive preferences and purchases of unhealthy beverages.8 Beverage companies frequently target their sugary drink advertising towards youth, and are more likely to target Black/African American and Latino youth. Additionally, Black/African American and Latino populations are less likely to be the audience for marketing of healthy drinks like water.8

Strong evidence links increased consumption of sugary drinks to higher risk for obesity and other diseases that are tied to what people eat, such as type 2 diabetes,9,10 and the prevalence of these diseases is higher among people with lower income and Latino and Black/African American Californians.7,11 An estimated 37% of adults11 and 21% of youth12 in California have obesity. If current trends continue, 42% of adults in the state will have obesity by 2030.11

Taxes have emerged as a promising strategy to reduce consumption of sugary drinks. In addition to the potential of a sugary drink tax to reduce obesity, it has cost implications as well. This report models the projected effect of a sugary drink excise tax on health, disease outcomes, and health care cost savings over the next decade.

Key Terms
  • Cost-saving: saves more in future health care costs than it costs to implement (not considering the potential revenues)

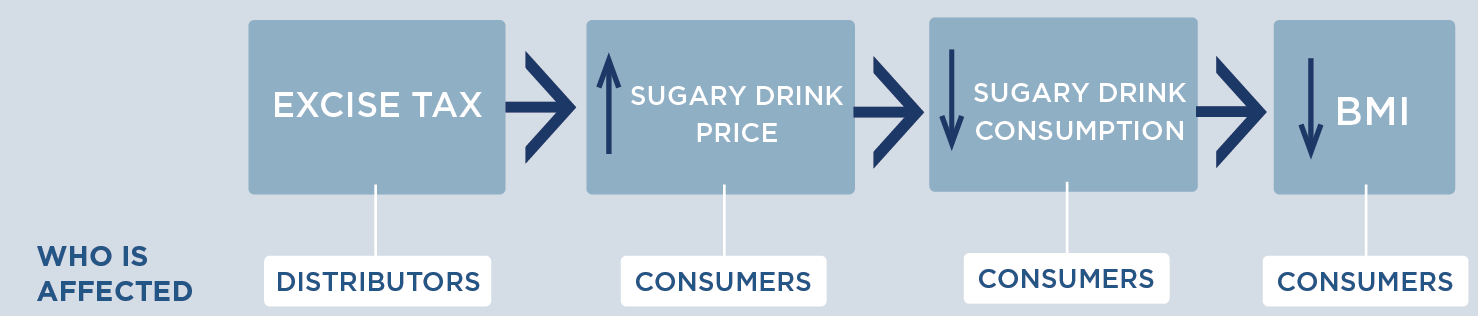
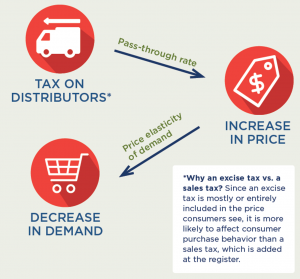
  • Excise tax: a consumption tax collected from retailers or distributors; it is reflected in the posted price (a sales tax in contrast is applied after purchase of the item)

  • Pass-through rate: how much of the excise tax on distributors is passed on to consumers as an increase in shelf price; a percent ranging from 0% (none of the tax) to 100% (all the tax), or even greater than 100% (more than the amount of the tax)

  • Price elasticity of demand: how much consumer purchasing behavior changes following a change in price of an item

Projected Impact of a Sugary Drink Excise Tax in California

We modeled implementation of a California excise tax on sugary drinks, at a tax rate of $0.02/ounce. All drinks with added caloric sweeteners were considered to be taxed, while 100% juice, milk products, and beverages with fewer than 25 kcals per 12 fluid ounces were considered exempt.


Results: What did we find?

We project that implementation of a state excise tax on sugary drinks only, at a tax rate of $0.02/ounce, has a 100% likelihood of being cost-saving. It will prevent more than 195,000 cases of childhood and adult obesity, prevent new cases of diabetes, increase healthy life years, improve health equity, and save more in future health care costs than it will cost to implement. Implementing the tax could also serve as a powerful social signal to reduce sugar consumption. Model results are presented as the most likely estimate as well as a likely range. The likely range is an uncertainty interval that is estimated by considering uncertainty from data sources and population projections and calculating a central range in which 95 percent of these model results fell.


How many people would be affected by the tax?

This can be thought of as reach or the number of people affected by the strategy. Based on our modeling, the table below presents the estimated number of people affected by the tax in the first year and the number of people affected by the tax over ten years.

Number of people affected by the tax

Likely Range

First Year Population Reach

38.0 million

37.9 million; 38.1 million

Ten Year Population Reach

42.2 million

42.0 million; 42.5 million

The Likely Range is a 95% uncertainty interval estimated by running the model 1,000 times, taking into account uncertainty from data sources and population projections, and calculating a central range in which 95 percent of these model results fell.

What effect would the tax have on sugary drink consumption and spending?

Compared to projections of sugary drink consumption without a tax, the tax is projected to result in lower levels of sugary drink consumption. We project a 90% likelihood that individuals and households who purchase sugary drinks will spend less on sugary drinks after the tax is implemented, even though sugary drink prices will be higher with the tax. 

Impact of the tax on sugary drink consumption & spending

Likely Range

Decrease in 12-oz Servings of Sugary Drinks per Person in the First Year

69

42; 125

Decrease in Spending on Sugary Drinks in the First Year per Person Consuming Sugary Drinks

$48

-$10; $170

90% likelihood of decrease in spending

Decrease in Spending on Sugary Drinks in the First Year per Household

$142

-$29; $502

90% likelihood of decrease in spending

Decrease in Spending on Sugary Drinks in the First Year Overall in California

$1.09 billion

-$220 million; $3.88 billion

90% likelihood of decrease in spending

The Likely Range is a 95% uncertainty interval estimated by running the model 1,000 times, taking into account uncertainty from data sources and population projections, and calculating a central range in which 95 percent of these model results fell.

Average Annual Pre-Tax Sugary Drink Consumption Per Person in California by Race/Ethnicity
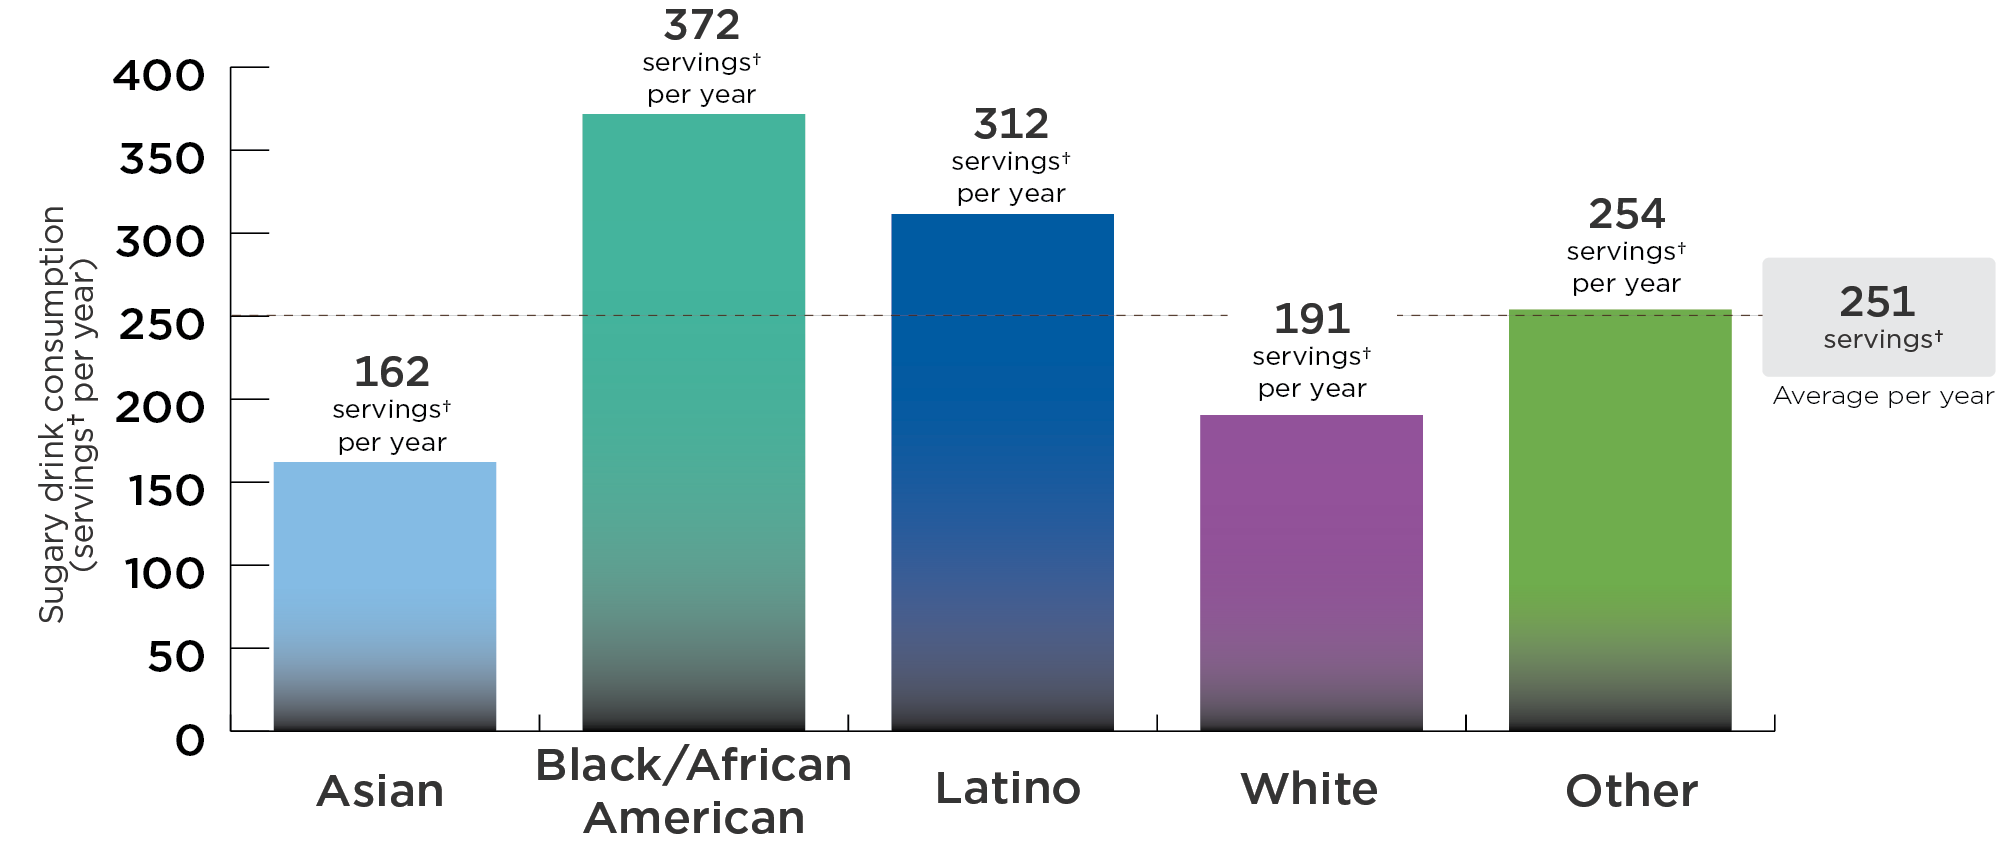
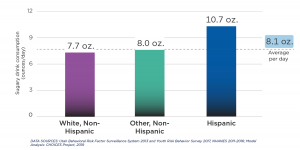
While Californians, on average, consume 251 servings of sugary drinks each in a year, higher than average sugary drink consumption levels are common among Latino and Black/African American Californians. Asian Californians drink an average of 162 12 ounce servings of sugary drinks per person per year; Black/African American Californians drink an average of 372 12 ounce servings of sugary drinks per person per year; Latino Californians drink an average of 312 12 ounce servings of sugary drinks per person per year; White Californians drink an average of 191 12 ounce servings of sugary drinks per person per year; and Californians of Other races drink an average of 254 12 ounce servings of sugary drinks per person per year
DATA SOURCES: California Health Interview Survey 2011-2017, NHANES 2011-2016, UConn Rudd Center for Food Policy & Obesity Sugary Drink Tax Calculator 2020; Analysis by CHOICES Project, 2020.
✝Each serving is 12 ounces.

While Californians, on average, consume 251 servings of sugary drinks each in a year, higher than average sugary drink consumption levels are common among Latino and Black/African American Californians.

Post-Tax Decrease in Sugary Drink Consumption Per Person in California by Race/Ethnicity*
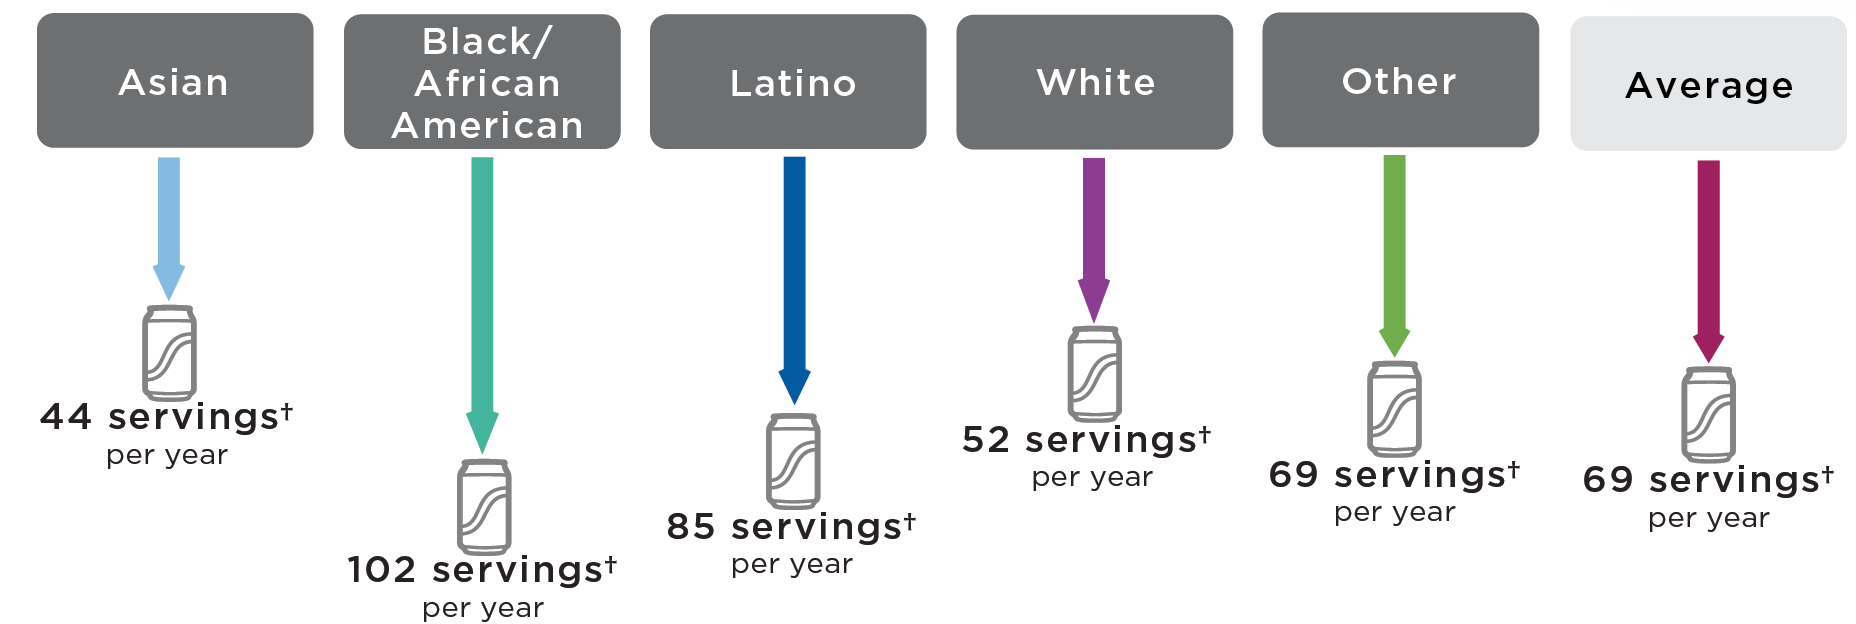
With a tax, sugary drink consumption would decrease the most among Latino and Black/African American Californians. On average, each Latino Californian would reduce consumption by 85 servings per year and each Black/African American Californian would reduce consumption by 102 servings per year. Asian Californians would reduce consumption an average of 44 12 ounce servings of sugary drinks per person per year; Black/African American Californians would reduce consumption an average of 102 12 ounce servings of sugary drinks per person per year; Latino Californians would reduce consumption an average of 85 12 ounce servings of sugary drinks per person per year; White Californians would reduce consumption an average of 52 12 ounce servings of sugary drinks per person per year; and Californians of Other races would reduce consumption an average of 69 12 ounce servings of sugary drinks per person per year

*In the first year following an excise tax of $0.02/ounce on sugary drinks.

✝Each serving is 12 ounces.

With a tax, sugary drink consumption would decrease the most among Latino and Black/African American Californians. On average, each Latino Californian would reduce consumption by 85 servings per year and each Black/African American Californian would reduce consumption by 102 servings per year.

Impact of the tax on sugary drink consumption, by race and ethnicity

Outcome

Asian

Mean

Likely Range

Black/African American

Mean

Likely Range

Latino

Mean

Likely Range

White

Mean

Likely Range

Other*

Mean

Likely Range

Decrease in 12-oz Servings of Sugary Drinks per Person in the First Year

44

27; 81

102

62; 186

85

52; 154

52

32; 98

69

42; 124

The Likely Range is a 95% uncertainty interval estimated by running the model 1,000 times, taking into account uncertainty from data sources and population projections, and calculating a central range in which 95 percent of these model results fell.
*Other includes people of Native Hawaiian and Pacific Islander, American Indian and Alaska Native, and two or more races.

What effect would the tax have on obesity and related health outcomes, overall and by race/ethnicity?

Compared to projections of obesity and related health outcomes without a tax, the tax is projected to result in fewer cases of obesity and fewer deaths over the 10-year period under consideration. Under the proposed tax, Black/African American Californians will experience a 39% higher than average reduction in obesity prevalence, and Latino Californians will experience a 33% higher than average reduction in obesity prevalence.

Impact of the tax on obesity and related health outcomes

Likely Range

Quality Adjusted Life Years (QALYs) Gained Over 10 Years

58,200

25,000; 130,000

Years of Life Gained Over 10 Years

14,600

5,410; 34,500

Deaths Prevented Over 10 Years*

4,280

1,680; 10,000

Years with Obesity Prevented Over 10 Years

1,410,000

696,000; 2,770,000

Cases of Obesity Prevented in 2030*

198,000

96,700; 394,000

Cases of Childhood Obesity Prevented in 2030*

33,700

12,500; 74,800

The Likely Range is a 95% uncertainty interval estimated by running the model 1,000 times, taking into account uncertainty from data sources and population projections, and calculating a central range in which 95 percent of these model results fell.
Costs and health outcomes are discounted at 3% per year, unless otherwise noted. Discounting estimates the present value of costs and health outcomes that are spent or received in the future, given that they are worth more today than they would be tomorrow.
*Not discounted.

$0.02 per ounce state excise tax on sugary drinks would lead to 198,000 cases of obesity prevented in 2030 and 33,700 cases of childhood obesity prevented in 2030


Pre-Tax Obesity Prevalence in California by Race/Ethnicity
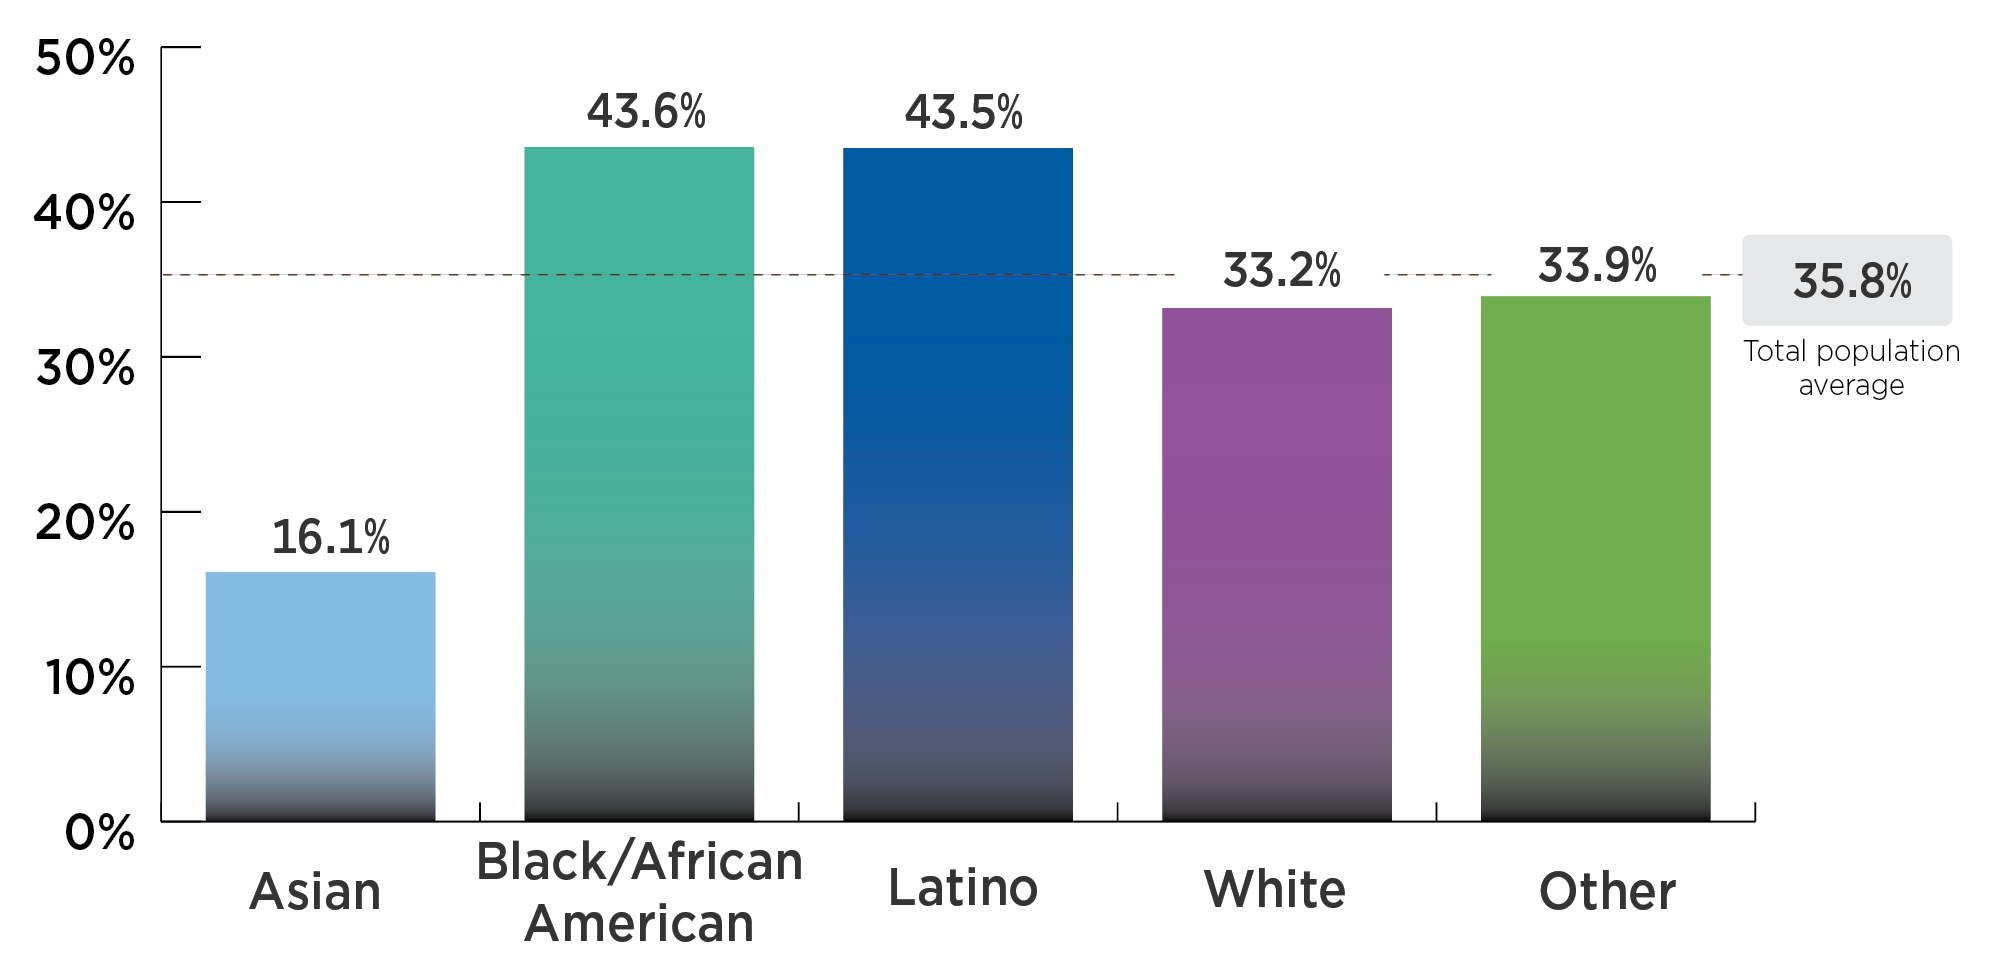
Nearly half of Latino (43.5%) and Black/African American (43.6%) Californians have obesity, while smaller percentages of Asian (16.1%), White (33.2%), and Californians of another race (33.9%) have obesity.
DATA SOURCES: California FitnessGram 2013-2017, NHANES 2011-2016, NSCH 2003-2018; Analysis by CDPH and the CHOICES Project, 2020.

Nearly half of Latino (43.5%) and Black/African American (43.6%) Californians have obesity, while smaller percentages of Asian (16.1%), White (33.2%), and Californians of another race (33.9%) have obesity.

Post-Tax Cases of Obesity Prevented in 2030 in California by Race/Ethnicity*
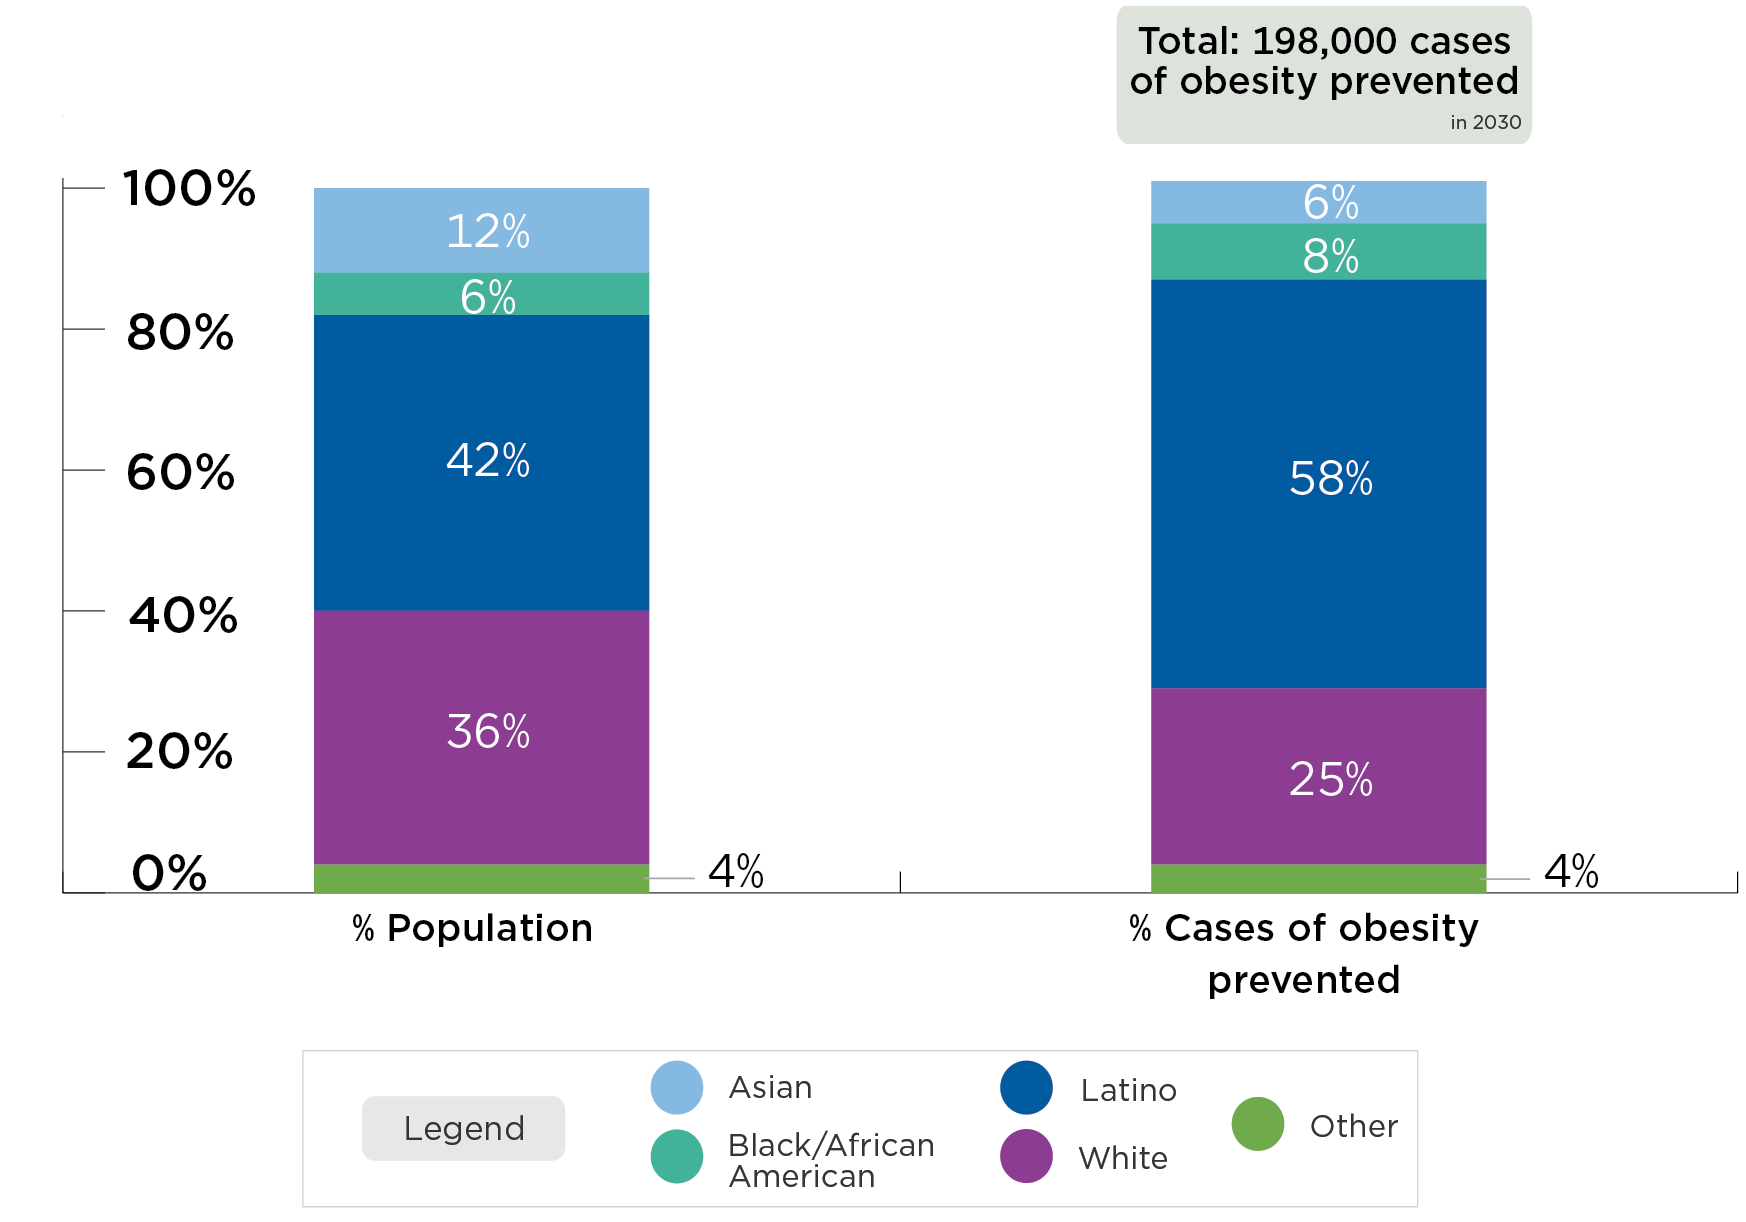
A tax in California could prevent 198,000 cases of obesity in 2030. 58% of prevented obesity cases will be among Latino Californians, while they represent 42% of the population. 8% of prevented obesity cases will be among Black/African American Californians, while they represent 6% of the population.


*With an excise tax of $0.02/ounce on sugary drinks.

A tax in California could prevent 198,000 cases of obesity in 2030. 58% of prevented obesity cases will be among Latino Californians, while they represent 42% of the population. 8% of prevented obesity cases will be among Black/African American Californians, while they represent 6% of the population.

Impact of the tax on behavior and health, by race/ethnicity

Outcome

Asian

Mean

Likely Range

Black/African American

Mean

Likely Range

Latino

Mean

Likely Range

White

Mean

Likely Range

Other†

Mean

Likely Range

QALYS Gained Over 10 Years

3,560

1,490; 8,160

5,100

1,990; 11,300

28,700

12,600; 64,200

18,900

7,810; 42,600

1,910

818; 4,230

Years of Life Gained Over 10 Years

893

128; 2,400

1,820

381; 4,470

5,330

1,720; 12,800

6,020

2,040; 14,900

506

0; 1,490

Years with Obesity Prevented Over 10 Years

80,800

39,800; 159,000

110,000

53,300; 218,000

820,000

407,000; 1.6 million

354,000

159,000; 751,000

47,100

23,300; 89,700

Cases of Obesity Prevented in 2030*

12,700

5,960; 26,500

15,100

7,130; 30,700

114,000

56,300; 218,000

49,800

22,400; 106,000

7,050

3,430; 13,500

Cases of Childhood Obesity Prevented in 2030*

1,700

571; 3,980

2,920

1,060; 6,560

24,200

8,920; 52,900

3,610

1,240; 8,740

1,260

428; 2,920

The Likely Range is a 95% uncertainty interval estimated by running the model 1,000 times, taking into account uncertainty from data sources and population projections, and calculating a central range in which 95 percent of these model results fell.
Costs and health outcomes are discounted at 3% per year, unless otherwise noted. Discounting estimates the present value of costs and health outcomes that are spent or received in the future, given that they are worth more today than they would be tomorrow.
*Not discounted.
✝Other includes people of non-Latino ethnicity and Native Hawaiian and Pacific Islander, American Indian and Alaska Native, and two or more races.

How much would the tax cost to implement?

There are initial and ongoing costs to implementing the tax. To implement the strategy, the California Department of Tax and Fee Administration would perform several administrative activities, including identifying and notifying taxpayers, revising manuals and tax return documents and systems, processing tax statements, and conducting audits. Businesses would also need to prepare tax statements and participate in audits, which would require labor from private tax accountants. Cost information was drawn from tax programs that were previously implemented in California13 and from planned or implemented excise taxes on sugary drinks in other states and localities.14 The cost and benefit estimates do not include expected tax revenue (discussed below). Below we include annual and 10-year implementation costs.

Costs

Likely Range

Annual Implementation Cost

$3.9 million

$2.69 million; $4.99 million

Annual Implementation Cost per Person

$0.10

$0.07; $0.13

Total Intervention Implementation Cost Over 10 Years

$39.0 million

$26.9 million; $49.9 million

The Likely Range is a 95% uncertainty interval estimated by running the model 1,000 times, taking into account uncertainty from data sources and population projections, and calculating a central range in which 95 percent of these model results fell.
Costs and health outcomes are discounted at 3% per year, unless otherwise noted. Discounting estimates the present value of costs and health outcomes that are spent or received in the future, given that they are worth more today than they would be tomorrow.

How much would the tax save in health care costs compared to what it costs to implement?

The estimated reduction in obesity attributable to the tax leads to lower projected health care costs, offsetting tax implementation costs and resulting in a net cost savings. The difference between total health care costs with no strategy and lower health care costs with a strategy represents health care costs saved; these savings can be compared to the cost of implementing the tax to arrive at the metric of health care costs saved per $1 invested.

Costs

Likely Range

Health Care Costs Saved Over 10 Years

$1.83 billion

$783 million; $4.06 billion

Net Costs Difference Over 10 Years

-$1.79 billion

-$4.03 billion; -$740 million

Health Care Costs Saved per $1 Invested Over 10 Years

$46.89

$19.82; $118.76

The Likely Range is a 95% uncertainty interval estimated by running the model 1,000 times, taking into account uncertainty from data sources and population projections, and calculating a central range in which 95 percent of these model results fell.
Costs and health outcomes are discounted at 3% per year, unless otherwise noted. Discounting estimates the present value of costs and health outcomes that are spent or received in the future, given that they are worth more today than they would be tomorrow.

What would the impact of the tax be on Medi-Cal* spending?

Based on the projected reduction in adult obesity prevalence due to the tax (compared to what prevalence would be without the tax), adult obesity-related Medi-Cal expenditures in California are estimated to decrease. This does not include potential reductions in child obesity-related expenditures, and may be an underestimate if adults utilizing Medi-Cal have higher than average health care costs of obesity.15 A previous analysis found that 12.2% of adult Medi-Cal expenditures were due to obesity.16 We estimate that, in California, obesity accounted for $8.9 billion of $73.3 billion total adult Medi-Cal expenditures in 2019.16,17 This assumes that 74% of all Medi-Cal payments are for adults.18 The state paid 37% of total Medi-Cal expenditures in 2019,17 so we estimate that the state paid $3.3 billion in adult obesity-related Medi-Cal expenditures.

*Medi-Cal is California’s Medicaid program

Medi-Cal Spending

Likely Range

Reduction in Annual Adult Obesity-Related Medi-Cal Expenditures (Paid by State)

$17.9 million

$8.19 million; $38.5 million

Reduction in Total Annual Adult Obesity-Related Medi-Cal Expenditures (Paid by State and Federal)

$48.3 million

$22.1 million; $104 million

The Likely Range is a 95% uncertainty interval estimated by running the model 1,000 times, taking into account uncertainty from data sources and population projections, and calculating a central range in which 95 percent of these model results fell.
Costs and health outcomes are discounted at 3% per year, unless otherwise noted. Discounting estimates the present value of costs and health outcomes that are spent or received in the future, given that they are worth more today than they would be tomorrow.

What are the key cost-effectiveness metrics?

Since we project that the tax saves more in future health care costs than it costs to implement, there is a 100% likelihood that the tax would be cost-saving. 

Cost-effectiveness metrics

Cost per Year with Obesity Prevented Over 10 Years

Cost-saving*

Cost per QALY Gained Over 10 Years

Cost-saving*

Cost per YL Gained Over 10 Years

Cost-saving*

Cost per Death Averted Over 10 Years

Cost-saving*

Costs and health outcomes are discounted at 3% per year, unless otherwise noted. Discounting estimates the present value of costs and health outcomes that are spent or received in the future, given that they are worth more today than they would be tomorrow.
*There is a 100% likelihood that these metrics are cost-saving.

What effect would the tax have on diabetes?

Economic studies indicate that with a sugary drink tax, consumers will buy less of these products.19 A $0.02/ounce tax will decrease the consumption of sugary drinks and this has other health implications that we can estimate. In California, the proposed sugary drink excise tax would lead to a 7% reduction in diabetes incidence over one year once the tax reaches full effect. We calculated this impact on diabetes incidence using projected declines in sugary drink consumption, not directly via microsimulation.$0.02 per ounce state excise tax on sugary drinks would lead to a 7% reduction in diabetes incidence and 13,900 cases of diabetes prevented

What effect would the tax have on tooth decay?

In California, we estimated that a $0.02/ounce tax would lead to a reduction of 502,000 decayed, missing, and filled teeth among Medi-Cal* recipients and $39.5 million in savings to Medi-Cal over 10 years due to a reduction in treatment of tooth decay. For the entire California population, we estimated the tax would lead to a reduction of 1,620,000 decayed, missing, and filled teeth and $135 million in savings for all payers due to a reduction in treatment of tooth decay. The Medi-Cal reimbursement tax estimates may underestimate the total cost savings of tooth decay treatment projected here as dental providers may charge higher amounts to patients. Impact on tooth decay was calculated using projected declines in sugary drink consumption, not directly via microsimulation.

*Medi-Cal is California’s Medicaid program

$0.02 per ounce state excise tax on sugary drinks would lead to $39.5 million in dental decay treatment cost savings over 10 years (Medi-Cal) and $135 million in dental decay treatment total cost savings over 10 years (Societal)

Key Considerations for Health Equity

Concerns have been raised regarding the impact of the tax on low-income households, because lower-income populations tend to consume more sugary drinks.20 Economic studies indicate that with a sugary drink tax, consumers will buy less of these products.19 This change in purchasing is substantial, so that consumers can be expected to spend less on sugary drinks after a tax is implemented. Using sales data from the Rudd Center Revenue Calculator for Sugary Drink Taxes,21 we project that individuals and households in California will spend less money on sugary drinks after a $0.02 per ounce tax: about $48 less per year per person, and $142 per year less for an average household. This would free up disposable income for other consumer purchases. A typical consumer in California who continues to consume these beverages after the tax is in place would be expected to pay tax of about $1.40 per week, or $73/year.

In addition to these changes in spending, health benefits are projected to be greatest among low-income individuals. We also project that greater health benefits will accrue among Latino and Black/African American California residents compared with White and Asian residents. Using data on sugary drink consumption in the CHOICES model, the average daily consumption of sugary drinks among people in California varies by race/ethnicity group (see pre-tax figures on pages 4 and 6). Under the proposed tax, we project that Black/African American Californians would see a 39% greater reduction in obesity prevalence than average, and Latino Californians would see a 33% greater reduction in obesity prevalence than average. On that basis, the proposed tax could decrease disparities in obesity outcomes and improve health equity.

These expected changes in consumption and health outcomes have led economists to conclude that low-income populations benefit substantially from sugary drink taxes.22

Implementation Considerations

A $0.02/ounce statewide excise tax on sugary drinks in California could raise as much as $1.3 to $1.8 billion in annual revenue.21 Revenue raised from a sugary drink tax could be reinvested in communities with low-income. For instance, in Berkeley, CA, revenue from a municipal sugary drink tax has been allocated for spending on school and community programs, many serving families with low-income or communities of color, to promote healthy eating, diabetes, and obesity prevention.23,24 Public support for such taxes generally increases with earmarking for preventive health activities.24

There is opposition from the food and beverage industry, which spends billions of dollars promoting their products.25 Relatively small beverage excise taxes are currently applied across many states. The proposed tax is likely to be sustainable if implemented based on the successful history of tobacco excise taxes. There is potential for a shift in social norms of sugary drink consumption based on evidence from tobacco control tax and regulatory efforts.26 


Modeling Assumptions and Summary of the CHOICES Microsimulation Model


How does an excise tax on distributors affect the price paid by consumers?

An excise tax is incorporated directly into a beverage’s shelf price. We assume 100% pass-through of the tax over 10 years and assume the tax rate would be adjusted annually for inflation. Our pass-through rate estimate is supported by empirical studies of excise taxes in Mexico and France that demonstrate near-complete pass-through rates to consumers27 and consistent evidence in the U.S. indicating that beverage taxes increase prices, although there is some variation by store type.28-31   

The expected change in sugary drink price was estimated based on national sugary drink prices32 and regional sales data for several categories of sugary drinks (i.e., soda, sports drinks, fruit drinks, energy drinks, sweetened teas, sweetened coffees, and enhanced water).21 In California, we assume the average price of sugary drinks is almost $0.09/ounce, so a $0.02/ounce tax would raise prices by 23%. This means that, for example, the price of a 12-ounce can of soda would increase from $1.06 to $1.30/can post-tax.

How does increasing the price of sugary drinks change individual sugary drink consumption?

How much consumers will change their purchases in response to price changes is called price elasticity for demand. We assume for every 10% increase in the price of sugary drinks, there will be a 12% reduction in purchases (a mean own-price elasticity of demand of -1.21).19 Recent research on the Berkeley, CA $0.01/ounce tax found a 21% reduction in sugary drink intake among populations with low-income consistent with this estimate.33-37 In California, we assume a $0.02/ounce tax that raises prices by 23% would reduce purchases by 27%. We assume this 27% reduction in purchases results in a 27% reduction in consumption.

To estimate current sugary drink consumption levels in California, we used national estimates of sugary drink consumption from NHANES 2011-2016 adjusted to race- and ethnicity-specific estimates of sugary drink consumption among children, teens, and adults from the California Health Interview Survey38 and estimates of sugary drink sales in California from the UConn Rudd Center for Food Policy & Obesity.21

What are the health effects of decreasing sugary drink consumption?

Research has shown that decreasing sugary drink consumption can have positive effects on health in youth and adults.

Assumptions about sugary drinks and obesity risk

We estimated the impact of a change in sugary drink intake on body mass index (BMI), accounting for dietary compensation, based on rigorous studies identified in evidence reviews.14 The relationship among adults was modeled based on the range of estimated effects from four large, multi-year longitudinal studies, which indicated that a one-serving reduction in sugary drinks was associated with a BMI decrease of 0.21 kg/m2 to 0.57 kg/m2 in adults over a 3-year period.39-42 Among youth, we used evidence from a double-blind randomized controlled trial conducted over 18 months, which found that an additional 8-ounce serving of sugary drinks led to a 2.2 pound greater weight gain.43

Assumptions about sugary drinks and diabetes risk

We estimated the impact of the tax-induced reduction in sugary drink intake on diabetes incidence for adults ages 18-79 years using a published meta-analysis of the relative risk of developing diabetes due to a one-serving change in sugary drink consumption44 as well as state-level estimates of diabetes incidence from the CDC Atlas 201645 and prevalence from the California Health Interview Survey 2017-2018.46 On average, each 8.5-ounce serving of sugary drinks per day increases the risk of diabetes by 18%.44

Assumptions about sugary drinks and tooth decay

We estimated the impact of a sugary drink excise tax on tooth decay and tooth decay treatment costs using a longitudinal analysis of the relationship between intake of sugars and tooth decay in adults. On average, for every 10 grams higher intake of sugar per day, there is an increase in decayed, missing and filled teeth (i.e., tooth decay) of approximately 0.10 over 10 years.47 There are many studies showing a similar relationship between higher intake of sugars and tooth decay in children and youth48 and thus we assume the same relationship as found in adults. We used the Medi-Cal Dental Provider Handbook 201949 to estimate a Medi-Cal cost of treating tooth decay as: $278 for a permanent crown and $58 for a filling. These codes reflect treatment for one to four surfaces but do not reflect the actual frequency of multi-surface treatment among Medi-Cal recipients or for higher reimbursement rates due to temporary crowns or potential flat tax schedules. Based on analysis of data on tooth decay, fillings and crowns for the U.S. population from NHANES 1988-1994 (the last year crowns and fillings were separately reported),50 we estimate that 78.9% of tooth decay in children and 43.5% of tooth decay in adults is treated. Using this same data set, we estimate that 97% of treatment for children is fillings and 82.5% of treatment for adults is fillings. To estimate Medi-Cal-specific savings in costs of dental treatment, we used estimates of the number of people enrolled in the Medi-Cal Dental Program in 2018.51

CHOICES Microsimulation Model

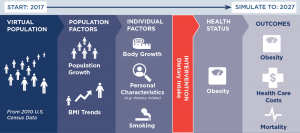
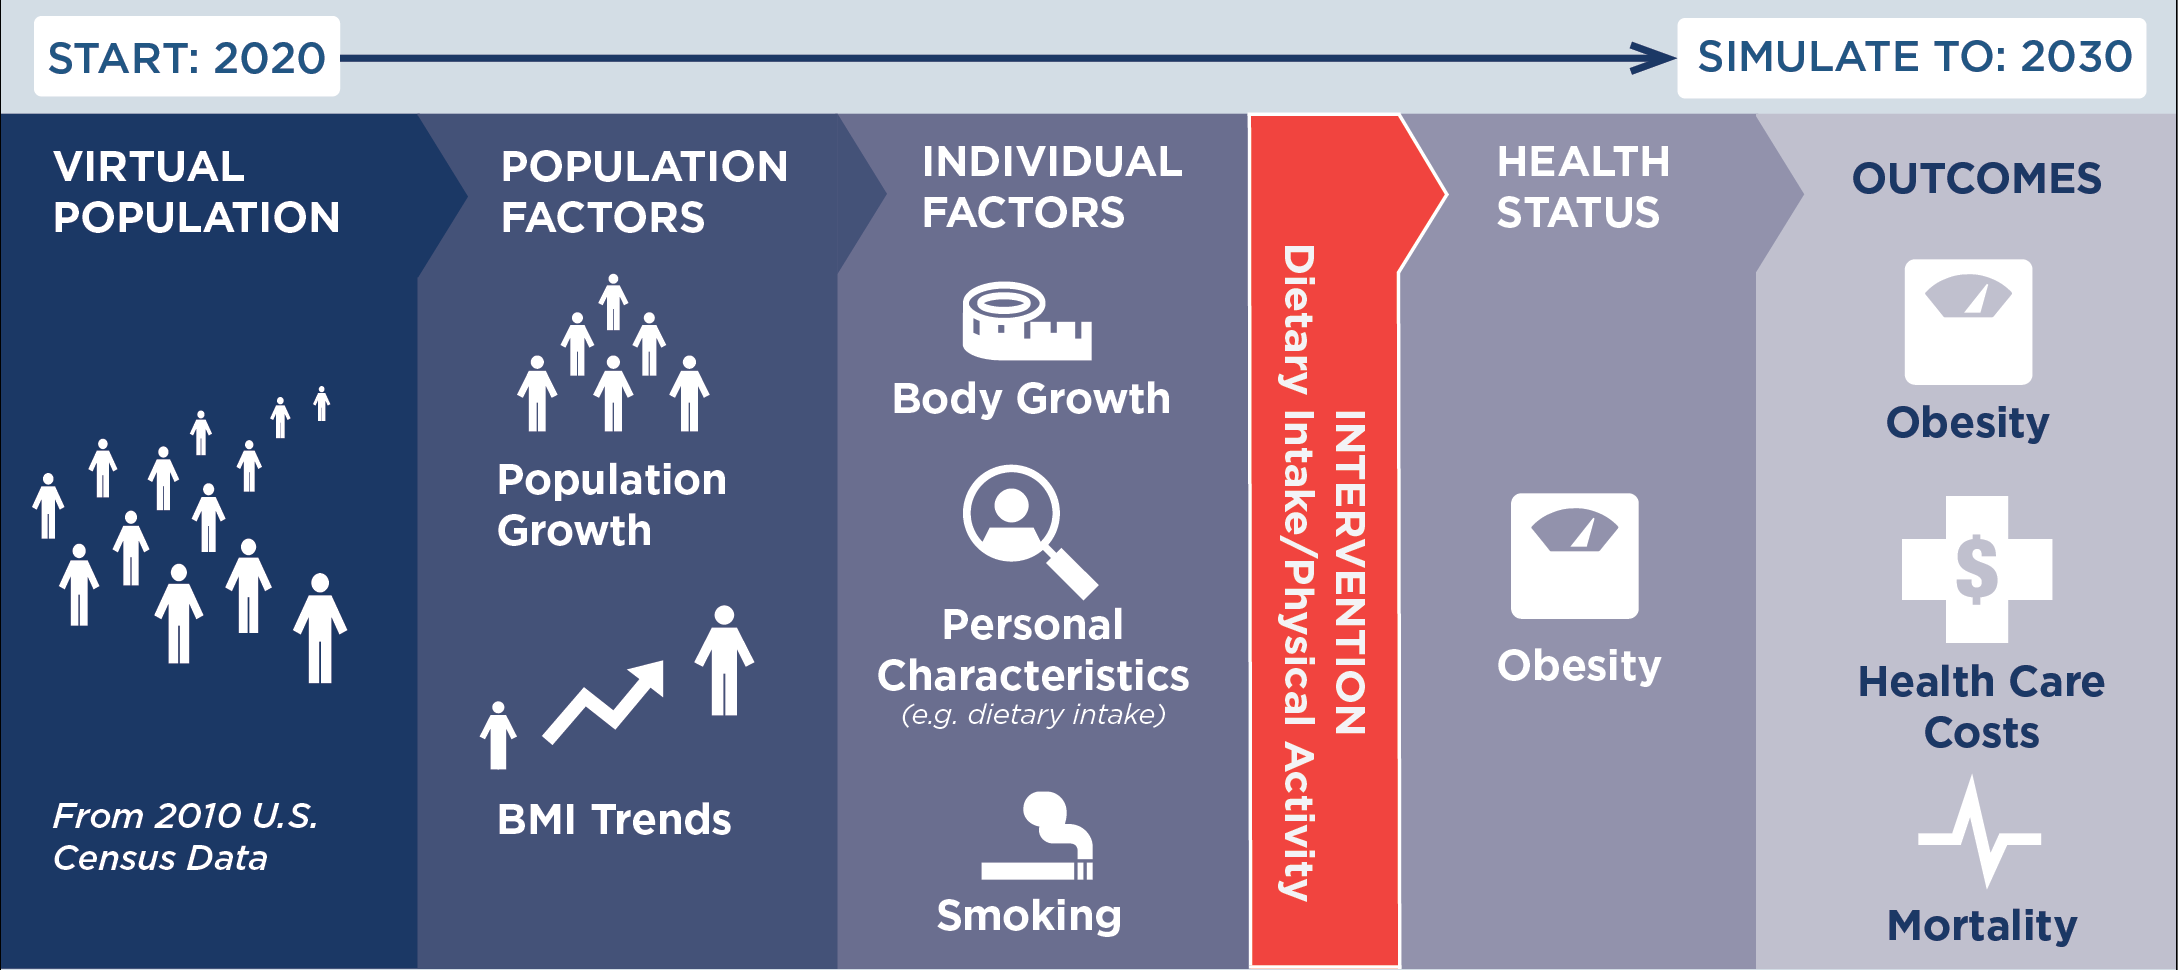
The CHOICES microsimulation model was used to calculate the costs and effectiveness of a tax in California over 10 years (2020-2030). We forecasted what would happen to a virtual population of residents in California with and without a sugary drink tax to model changes in disease and mortality rates and health care costs due to the tax. Cases of obesity prevented were calculated at the end of the model period in 2030. The model was based on peer-reviewed CHOICES methodology.14,52-54 We created a virtual population of residents in California using data from: the U.S. Census, American Community Survey, Behavioral Risk Factor Surveillance System, NHANES, National Survey of Children’s Health,52 the Medical Expenditure Panel Survey, multiple national longitudinal studies, and obesity prevalence data provided by California Department of Public Health. Impacts on diabetes, tooth decay, Medicaid spending, and household spending on sugary drinks were calculated based on summary results from the model, not directly via microsimulation.

Of note, the CHOICES microsimulation model does not include annual revenue generation from a state excise tax on sugary drinks in any of the cost-effectiveness calculations. The Rudd Center Revenue Calculator for Sugary Drink Taxes estimates potential annual revenues from excise taxes on sugary drinks and is “intended to provide a rough estimate” for municipalities to consider.21 According to the Rudd Center,21 a $0.02/ounce excise tax in California could raise as much as $1.8 billion in 2020. Accounting for 10-30% non-compliance as the Rudd Center advises, annual revenue estimates range between $1.3 – $1.8 billion.CHOICES microsimulation model: start in 2020 and simulate to 2030. Start with a virtual population using data from the 2010 U.S. census. Then take into account population factors, such as population growth and BMI trends. Then take into account individual factors, such as body growth, personal characteristics (e.g. dietary intake), and smoking. Then, input the intervention (dietary intake/physical activity). Then, look at health status (obesity) and outcomes (obesity, health care costs, and mortality).
Citation

Gouck J, Whetstone L, Walter C, Pugliese J, Kurtz C, Seavey-Hultquist J, Barrett J, McCulloch S, Reiner J, Garrone M, Cradock A, Gortmaker, S. California: A Sugary Drink Excise Tax. California Department of Public Health, Sacramento, CA, the County of Santa Clara Public Health Department, San Jose, CA, and the CHOICES Learning Collaborative Partnership at the Harvard T.H. Chan School of Public Health, Boston, MA; March 2021. For more information, please visit www.choicesproject.org

The design for this brief and its graphics were developed by Molly Garrone, MA and partners at Burness.

Funding

This work is supported by The JPB Foundation and the Centers for Disease Control and Prevention (U48DP006376). The findings and conclusions are those of the author(s) and do not necessarily represent the official position of the Centers for Disease Control and Prevention or other funders.

For further information, contact choicesproject@hsph.harvard.edu

← Back to Resources

References

  1. American Public Health Association Taxes on Sugar-Sweetened Beverages. 2012.
  2. Falbe J, Rojas N, Grummon AH, Madsen KA. Higher Retail Prices of Sugar-Sweetened Beverages 3 Months After Implementation of an Excise Tax in Berkeley, California. American Journal of Public Health. 2015;105(11):2194-2201.
  3. World Health Organization. Global action plan for the prevention and control of noncommunicable diseases 2013–2020 [Internet]. Geneva: WHO. Updated appendix 3, “Best buys” and other recommended interventions for the prevention and control of noncommunicable diseases; [updated 2017; cited 2019 Sep 17]. Available from: http://www.who.int/ncds/management/WHO_Appendix_BestBuys.pdf
  4. Hart A. New coalition calls for statewide soda tax in California. Politico. July 17, 2019. Accessed October 15, 2020 at: https://www.politico.com/states/california/story/2019/07/17/new-coalition-calls-for-statewide-soda-tax-in-california-1104414
  5. National Academies of Sciences, Engineering, and Medicine; Health and Medicine Division; Board on Population Health and Public Health Practice; Committee on Community-Based Solutions to Promote Health Equity in the United States; Baciu A, Negussie Y, Geller A, et al., editors. Communities in Action: Pathways to Health Equity. Washington (DC): National Academies Press (US); 2017 Jan 11. 3, The Root Causes of Health Inequity. Available from: https://www.ncbi.nlm.nih.gov/books/NBK425845
  6. U.S. Dept of Health and Human Services & U.S. Dept of Agriculture, 2015-2020 Dietary Guidelines for Americans, 8th Edition, 2015.
  7. UCLA Center for Health Policy Research. AskCHIS. 2017 Health Interview Survey. Available at: https://ask.chis.ucla.edu
  8. Harris JL, Fleming-Milici F, Kibwana-Jaff A, Phaneuf L. Sugary Drink FACTS 2020: Sugary drink advertising to youth: Continued barrier to public health progress. UConn Rudd Center for Food Policy & Obesity, June 2020. Accessed January 7, 2021 at http://sugarydrinkfacts.org/resources/Sugary%20Drink%20FACTS%202020/Sugary_Drink_FACTS_Full%20Report_final.pdf
  9. Malik VS, Pan A, Willett WC, Hu FB. Sugar-sweetened beverages and weight gain in children and adults: a systematic review and meta-analysis. American Journal of Clinical Nutrition. 2013;98(4):1084-1102. 16.
  10. Chen L, Caballero B, Mitchell DC, et al. Reducing Consumption of Sugar-Sweetened Beverages Is Associated with Reduced Blood Pressure: A Prospective Study among U.S. Adults. Circulation. 2010;121(22):2398-2406.
  11. Ward ZJ, Bleich SN, Cradock AL, Barrett JL, Giles CM, Flax CN, Long MW, Gortmaker SL. Projected U.S. State-Level Prevalence of Adult Obesity and Severe Obesity. New England Journal of  Medicine. 2019;381:2440-50. doi: 10.1056/NEJMsa1909301.
  12. California Department of Public Health, analysis of 2017 FitnessGram data provided by the California Department of Education.
  13. California Department of Tax and Fee Administration, personal communication to the California Department of Public Health, March 6, 2020.
  14. Gortmaker SL, Wang YC, Long MW, et al. Three Interventions That Reduce Childhood Obesity Are Projected To Save More Than They Cost To Implement. Health Affairs. 2015;34(11):1932-1939.
  15. Wang YC, Pamplin J, Long MW, Ward ZJ, Gortmaker SL, Andreyeva T. Severe Obesity In Adults Cost State Medicaid Programs Nearly $8 Billion In 2013. Health Affairs (Millwood). 2015 Nov;34(11):1923-31.
  16. Trogdon JG, Finkelstein EA, Feagan CW, Cohen JW. State- and payer-specific estimates of annual medical expenditures attributable to obesity. Obesity (Silver Spring). 2012 Jan;20(1):214-20.
  17. California Health Care Foundation. California Health Care Almanac, Medi-Cal Facts and Figures: Crucial Coverage for Low-Income Californians, February 2019. Accessed October 22, 2020 at: https://www.chcf.org/wp-content/uploads/2019/02/MediCalFactsFiguresAlmanac2019.pdf
  18. Lassman D, Hartman M, Washington B, Andrews K, Catlin A. US health spending trends by age and gender: selected years 2002-10. Health Affairs (Millwood). 2014 May;33(5):815-22.
  19. Powell LM, Chriqui JF, Khan T, Wada R, Chaloupka FJ. Assessing the Potential Effectiveness of Food and Beverage Taxes and Subsidies for Improving Public Health: A Systematic Review of Prices, Demand and Body Weight Outcomes. Obesity Reviews. 2013;14(2):110-128.
  20. Han E, Powell LM. Consumption patterns of sugar-sweetened beverages in the United States. Journal of the Academy of Nutrition and Dietetics. 2013;113(1):43-53.
  21. UConn Rudd Center for Food Policy & Obesity. Sugary Drink Tax Calculator. https://uconnruddcenter.org/tax-calculator. Accessed February 2021.
  22. Allcott H, Lockwood BB, Taubinsky D. Should We Tax Sugar-Sweetened Beverages? An Overview of Theory and Evidence. Journal of Economic Perspectives. 2019; 33 no 3: 202–27.
  23. Lynn J. City Council votes to allocate ‘soda tax’ revenue to school district, city organizations. The Daily Californian. Jan. 20, 2016; 2016.
  24. Berkeley City Council. (2016, June 14). Berkeley City Council meeting. [Annotated Agenda]. Retrieved from https://www.cityofberkeley.info/Clerk/City_Council/2016/06_June/City_Council__06-14-2016_-_Meeting_Info.aspx
  25. Federal Trade Commission. A review of food marketing to children and adolescents: follow-up report. Washington, DC; Dec 2012.
  26. Frieden TR, Mostashari F, Kerker BD, Miller N, Hajat A, Frankel M. Adult tobacco use levels after intensive tobacco control measures: New York City, 2002-2003. American Journal of Public Health. 2005;95(6):1016-1023
  27. Colchero MA, Salgado JC, Unar-Munguia M, Molina M, Ng SW, Rivera-Dommarco JA. Changes in Prices After an Excise Tax to Sweetened Sugar Beverages Was Implemented in Mexico: Evidence from Urban Areas. PLoS One. 2015;10(12):11.
  28. Cawley J, Frisvold D, Hill A, Jones D. The Impact of the Philadelphia Beverage Tax on Prices and Product Availability. NBER Working Paper. 2018(24990).
  29. Bleich SN, Lawman HG, LeVasseur MT, et al. The association of a sweetened beverage tax with changes in beverage prices and purchases at independent stores. Health Affairs (Millwood). 2020;39(7):1130-1139.
  30. Marinello S, Pipito AA, Leider J, Pugach O, Powell LM. The impact of the Oakland sugar-sweetened beverage tax on bottled soda and fountain drink prices in fast-food restaurants. Preventive Medicine Reports. 2020;17:101034.
  31. Ng S, Silver L, Ryan-Ibarra S, et al. Berkeley Evaluation of Soda Tax (BEST) Study Preliminary Findings. Presentation at the annual meeting of the American Public Health Association. Paper presented at: Presentation at the annual meeting of the American Public Health Association; November, 2015; Chicago, IL.
  32. Powell L, Isgor z, Rimkus L, Chaloupka F. Sugar-sweetened beverage prices: Estimates from a national sample of food outlets. Chicago, IL: Bridging the Gap Program, Health Policy Center, Institute for Health Research and Policy, University of Illinois at Chicago; 2014.
  33. Falbe J, Thompson HR, Becker CM, Rojas N, McCulloch CE, Madsen KA. Impact of the Berkeley Excise Tax on Sugar-Sweetened Beverage Consumption. American Journal of Public Health. 2016;106(10):1865-1871.
  34. Cawley J, Frisvold D, Hill A, Jones D. The impact of the Philadelphia beverage tax on purchases and consumption by adults and children. Journal of Health Economics. 2019;67:102225.
  35. Lee MM, Falbe J, Schillinger D, Basu S, McCulloch CE, Madsen KA. Sugar-Sweetened Beverage Consumption 3 Years After the Berkeley, California, Sugar-Sweetened Beverage Tax. American Journal of Public Health. 2019;109(4):637-639.
  36. Zhong Y, Auchincloss AH, Lee BK, Kanter GP. The Short-Term Impacts of the Philadelphia Beverage Tax on Beverage Consumption. American Journal of Preventive Medicine. 2018;55(1):26-34.
  37. Silver LD, Ng SW, Ryan-Ibarra S, et al. Changes in prices, sales, consumer spending, and beverage consumption one year after a tax on sugar-sweetened beverages in Berkeley, California, US: A before-and-after study. PLoS Medicine. 2017;14(4):e1002283
  38. 2011-2017 California Health Interview Survey data, analysis by the Harvard T.H. Chan School of Public Health, data provided by the UCLA Center for Health Policy Research, available at: http://healthpolicy.ucla.edu/chis/Pages/default.aspx
  39. Chen L, Caballero B, Mitchell DC, et al. Reducing Consumption of Sugar-Sweetened Beverages Is Associated with Reduced Blood Pressure: A Prospective Study among U.S. Adults. Circulation. 2010;121(22):2398-2406.
  40. Mozaffarian D, Hao T, Rimm EB, Willett WC, Hu FB. Changes in Diet and Lifestyle and Long-Term Weight Gain in Women and Men. New England Journal of Medicine. 2011;364(25):2392-2404.
  41. Palmer JR, Boggs DA, Krishnan S, Hu FB, Singer M, Rosenberg L. Sugar-Sweetened Beverages and Incidence of Type 2 Diabetes Mellitus in African American Women. Archives of Internal Medicine. 2008;168(14):1487-1492.
  42. Schulze MB, Manson JE, Ludwig DS, et al. Sugar-sweetened beverages, weight gain, and incidence of type 2 diabetes in young and middle-aged women. Journal of the American Medical Association. 2004;292(8):927-934.
  43. de Ruyter JC, Olthof MR, Seidell JC, Katan MB. A trial of sugar-free or sugar-sweetened beverages and body weight in children. New England Journal of Medicine. 2012;367(15):1397-1406.
  44. Imamura F, O’Connor L, Ye Z, et al. Consumption of sugar sweetened beverages, artificially sweetened beverages, and fruit juice and incidence of type 2 diabetes: systematic review, meta-analysis, and estimation of population attributable fraction. British Journal of Sports Medicine. 2016;50(8):496-U484.
  45. Centers for Disease Control and Prevention. Diabetes Atlas. Accessed 10/21/20 at: https://gis.cdc.gov/grasp/diabetes/DiabetesAtlas.html#
  46. 2017-2018 California Health Interview Survey data, analysis by the Harvard T.H. Chan School of Public Health, data provided by the UCLA Center for Health Policy Research, available at: http://healthpolicy.ucla.edu/chis/Pages/default.aspx
  47. Bernabe E, Vehkalahti MM, Sheiham A, Lundqvist A, Suominen AL. The Shape of the Dose-Response Relationship between Sugars and Caries in Adults. Journal of Dental Research. 2016;95(2):167-172.
  48. Sheiham A, James WPT. A new understanding of the relationship between sugars, dental caries and fluoride use: implications for limits on sugars consumption. Public Health Nutrition. 2014;17(10):2176-2184.
  49. California Department of Health Care Services, Medi-Cal Dental Provider Handbook 2019. Accessed October 19, 2020 at: https://dental.dhcs.ca.gov/Dental_Providers/Denti-Cal/Provider_Handbook
  50. Ward Z, et al. NHANES III Dental Examination: An Incisive Report. unpublished report; 2018.
  51. California Department of Health Care Services, Multi Year Medi-Cal Dental Measures Data by Age Groups Calendar Year 2013 to 2018. Accessed October 19, 2020 at: https://data.chhs.ca.gov/dataset/test-dhcs-multi-year-dental-measures-data-by-age-groups-calendar-year-2013-to-2015
  52. Ward ZJ, Long MW, Resch SC, Giles CM, Cradock AL, Gortmaker SL. Simulation of Growth Trajectories of Childhood Obesity into Adulthood. New England Journal of Medicine. 2017;377(22):2145-2153.
  53. Ward ZJ, Long MW, Resch SC, et al. Redrawing the US Obesity Landscape: Bias-Corrected Estimates of State-Specific Adult Obesity Prevalence. PLoS One. 2016;11(3):13.
  54. Long MW, Ward Z, Resch SC, et al. State-level estimates of childhood obesity prevalence in the United States corrected for report bias. International Journal of Obesity. 2016;40(10):1523-1528.

Brief: Supporting Healthy Food and Beverage Choices in Afterschool Programs in Allegheny County, Pennsylvania

Young boy eating a green apple

The information in this brief is intended only to provide educational information.

This brief summarizes a CHOICES Learning Collaborative Partnership model examining the potential impacts of a healthy snack policy in afterschool programs that already provide snacks through the National School Lunch Program or the Child and Adult Care Food Program.

The Issue

All children deserve the opportunity to grow up at a healthy weight. If current trends in childhood obesity continue, most of today’s children will have obesity at age 35.1 The health care costs of treating obesity-related conditions in adulthood were $147 billion in 2008.2 Snacks account for 25% of total calorie intake among most U.S. children and are frequently composed of sweet foods and sugar-sweetened drinks,3 beverages that increase the risk of excess weight gain.4 Promoting healthy food and beverage choices in afterschool programs is one opportunity to improve children’s diets and potentially reduce childhood obesity.5

In Allegheny County, nearly 10,000 children attend an afterschool program that typically allows participants to bring in snacks that they can consume during the program. When children bring in their own snacks to afterschool programs, those snacks are often less healthy than snacks served within federal reimbursable meal programs.6

About a Healthy Snack Policy

A policy that does not allow children to bring in their own snacks to afterschool programs and only offers healthy food and/or beverage choices that are part of federal reimbursable meal programs could support good nutrition. Snacks refer to both foods and beverages. In Allegheny County, UPMC Children’s Hospital of Pittsburgh, and Allegheny Partners for Out-of-School Time work with 120 sites across the county through Healthy Out-of-School Time and Quality Campaign. The majority of these sites (117) serve snacks though federal reimbursable meal programs, but allow children to bring in their own snacks. These sites could benefit from adopting a healthy snack policy. Activities to support adoption of this policy would include training site directors, who would in turn train program staff. During the academic year, Healthy Out-of-School Time and Quality Campaign site coordinators would provide technical assistance to support policy adoption.

Comparing Costs and Outcomes

CHOICES cost-effectiveness analysis compared the costs and outcomes of adopting a healthy snack policy in 117 Healthy Out-of-School Time and Quality Campaign afterschool programs over 10 years. Programs could adopt either a policy that does not allow children to bring in sugary drinks or a policy that does not allow children to bring in either sugary drinks or their own food to afterschool programs.

Implementing a healthy snack policy could support good nutrition and save families money. By the end of 2027:
An infographic about the healthy snack policy results. The bottom of the graphic shows increased numbers for a food and drink plan instead of only a drink plan. The food and drink results are: 4, 510 children would consume fewer unhealthy snacks; 50 cases of childhood obesity prevented; $1,690,000 saved by families.

Conclusions and Implications

Adopting a healthy snack policy could promote better health for children in afterschool programs and save families money. For some programs, it may be more feasible to adopt a policy addressing sugary drinks only. Clear evidence links sugary drink consumption to excess weight gain.4

We estimate that providing the training, technical assistance, communication, coordination, and monitoring in afterschool programs to support the adoption of a healthy snack policy that only addresses sugary drinks would cost $53,500 over 10 years. It could also result in $965,000 in savings for families ($243 per child) who are no longer purchasing beverages for their children to bring to afterschool. Those children who regularly bring sugary drinks to afterschool programs and attend Healthy Out-of-School Time and Quality Campaign afterschool programs that adopt a healthy snack policy could reduce sugary drink consumption by 10 ounces per day on those days they attend programming. In addition, 27 cases of childhood obesity could be prevented in 2027 and $53,900 in obesity-related health care costs could be saved. Afterschool programs adopting a healthy snack policy can support healthy nutrition habits for children and lay a foundation for better health.

References

  1. Ward ZJ, Long MW, Resch SC, Giles CM, Cradock AL, Gortmaker SL. Simulation of Growth Trajectories of Childhood Obesity into Adulthood. New England Journal of Medicine. 2017 Nov 30;377(22):2145-2153.
  2. Finkelstein EA, Trogdon JG, Cohen JW, Dietz W. Annual Medical Spending Attributable To Obesity: Payer-And Service-Specific Estimates. Health Affairs. 2009;28(5).
  3. Wang D, van der Horst K, Jacquier E, Eldridge AL. Snacking among US children: patterns differ by time of day. Journal of Nutrition Education and Behavior. 2016; 48(6), 369-375.
  4. Malik VS, Schulze MB, Hu FB. Intake of sugar-sweetened beverages and weight gain: a systematic review. American Journal of Clinical Nutrition. 2006;84(2):274–88.
  5. Khan LK, Sobush K, Keener D, Goodman K, Lowry A, Kakietek J, et al. Recommended community strategies and measurements to prevent obesity in the United States. MMWR Recomm Rep 2009;58(RR-7):1–26.
  6. Kenney EL, Austin SB, Cradock AL, Giles CM, Lee RM, Davison KK, Gortmaker SL. Identifying sources of children’s consumption of junk food in Boston after-school programs, April-May 2011. Preventing Chronic Disease. 2014 Nov 20;11:E205
Suggested Citation:

Pagnotta M, Hardy H, Burry K, Flax CN, Barrett JL, Cradock AL. Allegheny County, PA: Supporting Healthy Food and Beverage Choices in Afterschool Programs {Issue Brief}. Allegheny County Health Department, Pittsburgh, PA, and the CHOICES Learning Collaborative Partnership at the Harvard T.H. Chan School of Public Health, Boston, MA; November 2019.

The design for this brief and its graphics were developed by Molly Garrone, MA and partners at Burness.

This issue brief was developed at the Harvard T.H. Chan School of Public Health in collaboration with the Allegheny County Health Department (ACHD) through participation in the Childhood Obesity Intervention Cost-Effectiveness Study (CHOICES) Learning Collaborative Partnership. This brief is intended for educational use only. Funded by The JPB Foundation. Results are those of the authors and not the funders.

← Back to Resources

Brief: Active Physical Education (PE) in Allegheny County, Pennsylvania

The information in this brief is intended only to provide educational information.

This brief summarizes findings from the CHOICES Learning Collaborative Partnership simulation model of implementing an Active Physical Education (PE) program in school districts participating in the Live Well Allegheny initiative in Allegheny County, Pennsylvania. Live Well Allegheny Schools will commit that 50% of PE class time be dedicated to moderate-to-vigorous physical activity (MVPA).

The Issue

One objective of the Allegheny County Health Department (ACHD) Community Health Improvement Plan is to decrease obesity in school-age children. Research shows that physical activity helps kids grow up at a healthy weight and reduces the risk of future chronic disease.1 However, many kids do not get enough daily physical activity,2 and without action, a majority of today’s children will have obesity at age 35.3 This has substantial financial implications. The health care costs for treating obesity-related health conditions like heart disease and diabetes were $147 billion in 2008.4

PE programs in schools can help students get the recommended amount of physical activity per day.1 However, research shows that children often spend less than half of PE class being physically active.5 Improving the quality of PE classes in ways that ensure that children are more active during class time will not only help children get more physical activity, but can also encourage children to develop habits to ensure an active and healthy lifestyle.1 The purpose of this study is to estimate the cost-effectiveness of implementing Active PE, which requires that at least 50% of PE class time be spent in MVPA.

About Active PE

The ACHD envisions that Active PE could be implemented in school districts that have partnered with Live Well Allegheny, a county-wide campaign to improve the health and wellness of Allegheny County residents. Implementation of Active PE would include dissemination of the evidence-based program SPARK PE to eligible elementary and middle schools. SPARK is a well-evaluated and widely used curriculum and training program that has been found to increase MVPA time in PE class.6

SPARK trainers would lead two-day workshops to train PE teachers on how to use and implement the SPARK PE curriculum. Participating schools would receive SPARK curricula, instructional materials, and equipment. Implementation would include a county-level PE Educational Specialist to provide oversight and monitoring of policy implementation, as well as ongoing training and support for teachers and schools each year.

Comparing Costs and Outcomes

CHOICES cost-effectiveness analysis compared the costs and outcomes of the implementation of the Active PE program in designated Live Well Allegheny school districts over a 10-year time horizon with the costs and outcomes of not implementing the intervention. We assumed that all elementary and middle schools serving grades K-8 that are part of the 18 designated Live Well Allegheny school districts would receive training from SPARK. The model assumes that 70% of the PE teachers trained would implement Active PE program in their schools.7,8

Implementing Active PE is an investment in the future. By the end of 2027:
An infographic about the results of active PE implimentation.

Conclusions and Implications

The implementation of Active PE using the evidence-based program SPARK within Live Well Allegheny Schools is projected to improve the health of many children in Allegheny County. The intervention would help ensure that 62,100 children attend schools with more active PE classes and would cost $2.29 million dollars to implement over 10 years, at an average of $37 per child. In schools that implement the Active PE program, on average we estimate that students would get 7 additional minutes of MVPA per school week, which is a 3% increase in MVPA. We estimate there will be 13 fewer cases of childhood obesity in the final year of the model as a result of implementation of Active PE.

SPARK training offers a professional development opportunity for teachers to improve instructional strategies to foster a fun and enjoyable environment where children can gain lifelong skills to engage in physical activity.10 There are also other likely positive benefits from physical activity related to improved bone health, aerobic and muscular fitness, cognition, and academic performance1 that are not quantified in this analysis but are important outcomes for children’s education and well-being.

Active PE is one evidence-based strategy that can benefit the majority of students in a school where most children attend PE classes and can be incorporated into a comprehensive plan to address childhood obesity. Leaders should use the best available evidence to select strategies to help children be more active.

References

  1. 2018 Physical Activity Guidelines Advisory Committee. 2018 Physical Activity Guidelines Advisory Committee Scientific Report. Washington, DC: U.S. Department of Health and Human Services, 2018. Accessed September 7, 2018.

  2. Child and Adolescent Health Measurement Initiative. 2016-2017 National Survey of Children’s Health (NSCH) data query. Data Resource Center for Child and Adolescent Health supported by Cooperative Agreement U59MC27866 from the U.S. Department of Health and Human Services, Health Resources and Services Administration’s Maternal and Child Health Bureau (HRSA MCHB). Retrieved [02/08/2019] from www.childhealthdata.org.

  3. Ward ZJ, Long MW, Resch SC, Giles CM, Cradock AL, Gortmaker SL. Simulation of Growth Trajectories of Childhood Obesity into Adulthood. New England Journal of Medicine. 2017; 377(22): 2145-2153.

  4. Finkelstein EA, Trogdon JG, Cohen JW, Dietz W. Annual Medical Spending Attributable To Obesity: Payer-And Service-Specific Estimates. Health Affairs. 2009;28(5).

  5. Institute of Medicine. Educating the Student Body: Taking Physical Activity and Physical Education to School. Washington, DC: National Academies Press; 2013.

  6. Sallis JF, McKenzie TL, Alcaraz JE, Kolody B, Faucette N, & Hovell MF. (1997). The effects of a 2-year physical education program (SPARK) on physical activity and fitness in elementary school students. Sports, Play and Active Recreation for Kids. American Journal of Public Health, 87(8), 1328-1334.

  7. Hoelscher DM, Feldman HA, Johnson CC, et al. School-based health education programs can be maintained overtime: results from the CATCH Institutionalization study. Prev Med. May 2004;38(5):594-606.

  8. McKenzie TL, Li D, Derby CA, Webber LS, Luepker RV, Cribb P. Maintenance of effects of the CATCH physical education program: results from the CATCH-ON study. Health Education Behavior. Aug 2003;30(4):447-462.

  9. Cradock AL, Barrett JL, Kenney EL, Giles CM, Ward ZJ, Long MW, … & Gortmaker SL. Using cost-effectiveness analysis to prioritize policy and programmatic approaches to physical activity promotion and obesity prevention in childhood. Preventive Medicine. 2017; 95, S17-S27.

  10. Society of Health and Physical Educators (SHAPE). Physical Education Guidelines. Retrieved from: https://www.shapeamerica.org/standards/guidelines/peguidelines.aspx. Accessed 13 April 2018.

  11. McKenzie TL, Sallis JF, & Rosengard P. (2009). Beyond the stucco tower: Design, development, and dissemination of the SPARK physical education programs. Quest, 61(1), 114-127.

Suggested Citation:

Pagnotta M, Hardy H, Reiner JF, Barrett JL, Cradock AL. Allegheny County, PA: Active Physical Education (PE) {Issue Brief}. Allegheny County Health Department, Pittsburgh, PA, and the CHOICES Learning Collaborative Partnership at the Harvard T.H. Chan School of Public Health, Boston, MA; December 2019.

The design for this brief and its graphics were developed by Molly Garrone, MA and partners at Burness.

This issue brief was developed at the Harvard T.H. Chan School of Public Health in collaboration with the Allegheny County Health Department (ACHD) through participation in the Childhood Obesity Intervention Cost-Effectiveness Study (CHOICES) Learning Collaborative Partnership. This brief is intended for educational use only. Funded by The JPB Foundation. Results are those of the authors and not the funders.

← Back to Resources

Brief: Safe Routes to School (SRTS) in Houston, Texas

Kids crossing street with crossing guard

The information in this brief is intended only to provide educational information.

This brief summarizes findings from the CHOICES Learning Collaborative Partnership simulation model of implementing Safe Routes to School (SRTS) initiatives in elementary and middle schools in Houston Independent School District. SRTS aims to help children safely walk and bicycle to school through infrastructure improvements, education, and promotional activities.

The Issue

Research shows that physical activity helps kids grow up at a healthy weight and reduces the risk of future chronic disease;1 however, many kids do not get enough daily physical activity,2 and without action, a majority of today’s children will have obesity at age 35.3 This has substantial financial implications. The healthcare costs for treating obesity-related health conditions like heart disease and diabetes were $147 billion in 2008.4

Every child deserves the opportunity to be healthy, and all kids need opportunities to be physically active, no matter where they live or where they go to school. Over recent decades, the declining rates of using physically active transportation modes like walking and bicycling to school may have contributed to lower than recommended levels of physical activity among youth.5 In Houston, concerns over pedestrian and bicycle safety may deter parents from allowing their child walk or bike to school. SRTS initiatives are an effective strategy to increase physical activity by promoting safer walking and bicycling opportunities6 and would be an important component of the City’s effort to create safe, efficient and effective alternatives to traveling by car.

About Safe Routes to School

Houston envisions implementing SRTS as part of Houston’s Vision Zero initiative, a comprehensive approach to address traffic safety to eliminate all traffic fatalities and serious injuries. Vision Zero can support SRTS initiatives to improve street safety and encourage more kids and families to walk and bike to and from school.

We estimated the cost to implement SRTS initiatives in Houston, including transportation infrastructure projects to improve the local physical environments around schools and education, encouragement and enforcement activities. Other necessary resources include a program coordinator and a Committee Taskforce to provide city-level oversight, administration, and project selection support.

Comparing Costs and Outcomes

CHOICES cost-effectiveness analysis compared the costs and outcomes over a 10-year time horizon (2017-2027) of implementing SRTS in Houston with the costs and outcomes associated with not implementing the program. We estimated that 199 elementary and middle schools serving grades K-8 in Houston Independent School District would implement a new SRTS program. Additional research suggests that 5.5% of students would shift from cars to active travel modes after SRTS implementation.6 This shift would result in some projected cost savings due to reduced vehicle use for school transportation trips.

Implementing Safe Routes to School in Houston is an investment in the future. By the end of 2027:
An infographic about implementing safe school routes. The graphic indicates 15,500 children would walk or bike to school.

Conclusions and Implications

Investing in initiatives that make it safer and more appealing to walk or bicycle to and from school can help more children accumulate recommended levels of physical activity. We estimate that over ten years, over 276,000 students in the Houston Independent School District would benefit from improved safety around schools and those that start walking or biking to school would engage in 48 more minutes of physical activity during the school week.

Implementing SRTS in Houston Independent School District would require an investment of $19.5 million dollars over 10 years. When accounting for cost offsets due to reduced vehicle traffic for students who shift travel modes, the projected 10-year implementation costs are estimated to be cost-saving. In Houston, SRTS project implementation costs could be offset by savings associated with reduced vehicle travel that include $4 million in environment-related cost savings. Additionally, families whose students start walking or bicycling and thus drive less for school transportation trips could average $1,080 in savings.

SRTS initiatives, which include a combination of infrastructure improvements (e.g., adding sidewalks or traffic calming) and non-infrastructure activities (e.g., safety education, promotional events, enforcement and evaluation activities) may also reduce the risk of pedestrian and bicycle injury.7,8 Investing in SRTS projects that make walking and bicycling to school safer and easier opens opportunities for those families who want to allow their child to walk or bike but cannot because of safety concerns.9

These multiple benefits reinforce the importance of investing in effective strategies that promote accessible, safe, and convenient walking and biking options to improve the health of our students and the environments of our local communities.

References

  1. 2018 Physical Activity Guidelines Advisory Committee. 2018 Physical Activity Guidelines Advisory Committee Scientific Report. Washington, DC: U.S. Department of Health and Human Services, 2018. Accessed September 7, 2018.
  2. Child and Adolescent Health Measurement Initiative. 2016-2017 National Survey of Children’s Health (NSCH) data query. Data Resource Center for Child and Adolescent Health supported by Cooperative Agreement U59MC27866 from the U.S. Department of Health and Human Services, Health Resources and Services Administration’s Maternal and Child Health Bureau (HRSA MCHB). Retrieved [02/08/2019] from www.childhealthdata.org.
  3. Ward ZJ, Long MW, Resch SC, Giles CM, Cradock AL, Gortmaker SL. Simulation of Growth Trajectories of Childhood Obesity into Adulthood. N Engl J Med. 2017; 377(22): 2145-2153.
  4. Finkelstein EA, Trogdon JG, Cohen JW, Dietz W. Annual Medical Spending Attributable To Obesity: Payer-And Service-Specific Estimates. Health Affairs. 2009;28(5).
  5. McDonald NC. Active transportation to school: trends among US schoolchildren, 1969–2001. American Journal of Preventive Medicine. 2007; 32(6), 509-516
  6. McDonald NC, Steiner RL, Lee C, Smith TR, Zhu X, & Yang Y. Impact of the Safe Routes to School Program on Walking and Bicycling, Journal of the American Planning Association. 2014; 80:2, 153-167
  7. DiMaggio C & Li G. Effectiveness of a safe routes to school program in preventing school-aged pedestrian injury. Pediatrics. 2013; 131(2), 290-296.
  8. DiMaggio C, Chen Q, Muennig PA, Li G. Timing and effect of a safe routes to school program on child pedestrian injury risk during school travel hours: Bayesian changepoint and difference-in-difference analysis. Injury Epidemiology 2014; 1:17
  9. McDonald NC & Aalborg AE. Why Parents Drive Children to School: Implications for Safe Routes to School Programs, Journal of the American Planning Association. 2009; 75:3, 331-342, DOI: 10.1080/01944360902988794
Suggested Citation:

Reiner JF, Barrett JL, Giles CM, Cradock AL. Houston, TX: Safe Routes to School {Issue Brief}. Houston Health Department, Houston, TX and the CHOICES Learning Collaborative Partnership at the Harvard T.H. Chan School of Public Health, Boston, MA; December 2019.

The design for this brief and its graphics were developed by Molly Garrone, MA and partners at Burness.

This issue brief was developed at the Harvard T.H. Chan School of Public Health in collaboration with the Houston Health Department and the Houston Planning and Development Department through participation in the Childhood Obesity Intervention Cost-Effectiveness Study (CHOICES) Learning Collaborative Partnership. This brief is intended for educational use only. Funded by The JPB Foundation. Results are those of the authors and not the funders.

← Back to Resources

Brief: Healthy Incentives Program within the SNAP in Harris County, Texas

The information in this brief is intended only to provide educational information.

This brief summarizes a CHOICES Learning Collaborative Partnership simulation model of a Healthy Incentives Program (HIP) in Harris County, TX that aims to increase fruit and vegetable consumption among Supplemental Nutrition Assistance Program (SNAP) recipients by providing a financial incentive of $0.30 for every $1 spent on fruits and vegetables.

The Issue

Over the past three decades, more and more people have developed obesity.1 The health care costs of treating obesity-related conditions in adulthood were $147 billion in 2008.2 As a strategy to reduce the risk of obesity and chronic disease, public health authorities emphasize the goal of increasing fruit and vegetable intake.3

In Harris County, nearly 69% of adults have too much excess weight.4 Nearly 265,000 adult Harris County residents are eligible for SNAP benefits.5 SNAP is a key strategy for reducing food insecurity among low-income populations. Regardless of SNAP participation, household purchases of fruits and vegetables are low.6 And, compared to eligible nonparticipants, SNAP participants may have a lower diet quality. Interventions may be needed that support the consumption of healthy foods like fruits and vegetables.7 Financial incentives are a proven strategy in increasing fruit and vegetable purchases.8,9

About the Healthy Incentives Program

Under this program, SNAP participants will receive an incentive of $0.30 for every $1 of SNAP benefits that they spend on targeted fruits and vegetables in SNAP-authorized grocery stores and farmers markets. Targeted fruits and vegetables include fresh, canned, frozen, and dried fruits and vegetables without added sugars, fats, oils, or salt, but exclude white potatoes and 100% fruit juice. SNAP participants will be automatically enrolled in the program; then, the incentive will be automatically credited back to the participants’ SNAP account after each household purchase of these products. The incentive will be capped at $60 per household per month to prevent misuse.

Comparing Costs and Outcomes

CHOICES cost-effectiveness analysis compared the costs and outcomes of providing SNAP participants with an incentive of $0.30 for every $1 of SNAP benefits that they spend on targeted fruits and vegetables in SNAP-authorized grocery stores and farmers markets over a 10-year time horizon with the costs and outcomes expected if no incentive is provided.

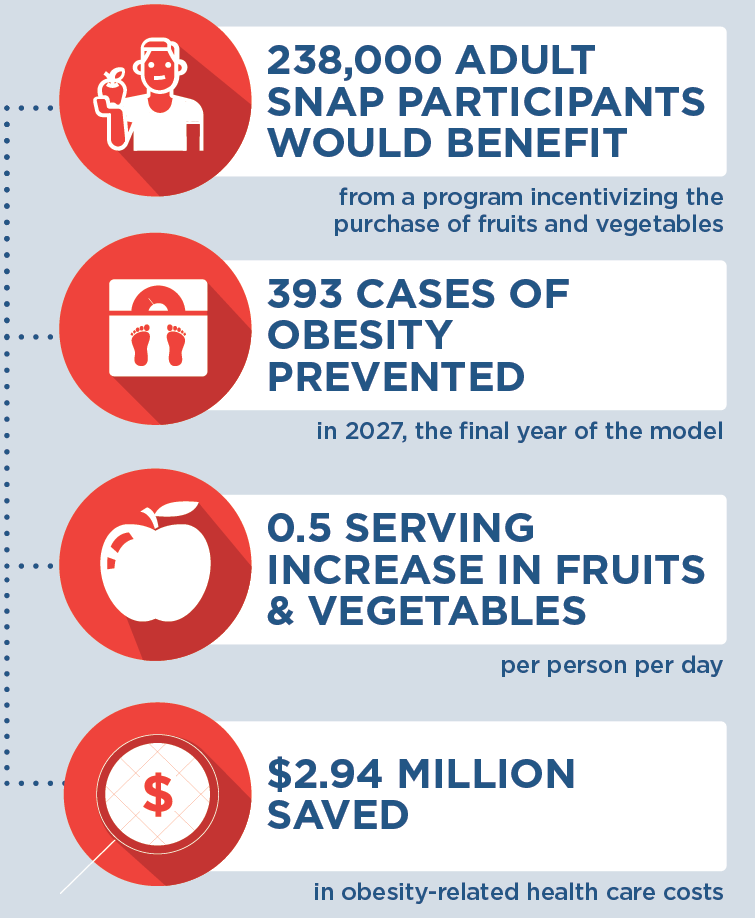
Implementing a Healthy Incentives Program in Harris County could increase fruit and vegetable purchases and improve health. By the end of 2027:
An infographic about the obesity and financial benefits of the fruit and vegetable incentive.

Conclusions and Implications

Providing SNAP participants with an incentive of $0.30 for every $1 of SNAP benefits that they spend on targeted fruits and vegetables in SNAP-authorized grocery stores and farmers markets could have a positive impact on health of the SNAP participants. This strategy could increase purchases of fruits and vegetables by more than 3 servings per week per person (a 36% increase)10 and promote better diet quality among participants. While not quantified here, this strategy may also increase fruit and vegetable consumption among children in households participating in SNAP.

A program incentivizing the purchase of fruits and vegetables among SNAP participants would require an investment of $479 per adult. For every $1.00 invested in implementing a Healthy Incentives Program, $0.03 in obesity-related health care costs would be saved. This strategy would prevent 393 cases of obesity in Harris County in 2027. Evidence is growing about how food pricing and incentive programs may help promote healthy diets and reduce the prevalence of obesity. These findings reinforce the importance of investing in preventive efforts that could have widespread community impact.

References

  1. Flegal MK, Kruszon-Moran D, Carroll MD, Fryar CD, Ogden CL. (2016). Trends in Obesity Among Adults in the United States, 2005 to 2014. JAMA, 315(21), 2284-91.

  2. Finkelstein EA, Trogdon JG, Cohen JW, Dietz W. (2009). Annual Medical Spending Attributable To Obesity: Payer-And Service-Specific Estimates. Health Affairs. 28(5).

  3. U.S. Department of Health and Human Services. (2010). Healthy people 2020 (2nd ed.). Washington, DC: U.S. Government Printing Office. U.S. Department of Agriculture and U.S. Department of Health and Human Services. (2010). Dietary guidelines for Americans, 2010 (7th ed.). Washington, DC: U.S. Government Printing Office.

  4. Texas Department of State Health Services. Texas Behavioral Risk Factor Surveillance System. 2014

  5. Texas Health and Human Services Commission. (2019)

  6. Grummon A & Taillie L. (2017). Nutrition profile of Supplemental Nutrition Assistance Program household food and beverages purchases. Am J Clin Nutr, 105(6). 1433-1442.

  7. Andreyeva T., Tripp A., Schwartz, M. (2015). Dietary Quality of Americans by Supplemental Nutrition Assistance Program Participation Status: A Systematic Review. Am J Prev Med. 49(4):594-604.

  8. Sturm R, An R, Segal D, Patel D. (2013). A cash-back rebate program for healthy food purchases in South Africa: results from scanner data. Am J Prev Med. 44(6):567-572.

  9. Gittelsohn J, Trude ACB, Kim H. Pricing Strategies to Encourage Availability, Purchase, and Consumption of Healthy Foods and Beverages: A Systematic Review. Prev Chronic Dis 2017;14:170213. DOI: https://www.doi.org/10.5888/pcd14.170213.

  10. Zhang FF, Liu J, Rehm CD, Wilde P, Mande JR, & Mozaffarian D. (2018). Trends and disparities in diet quality among US adults by Supplemental Nutrition Assistance Program participation status. JAMA network open, 1(2), e180237-e180237.

Suggested Citation:

Flax CN, Barrett JL, and Cradock AL. Houston Healthy Incentives Program within the Supplemental Nutrition Assistance Program in Harris County, TX {Issue Brief}. Houston Health Department, Houston, TX and the CHOICES Learning Collaborative Partnership at the Harvard T.H. Chan School of Public Health, Boston, MA; December 2019.

The design for this brief and its graphics were developed by Molly Garrone, MA and partners at Burness.

This issue brief was developed at the Harvard T.H. Chan School of Public Health in collaboration with the Houston Health Department through participation in the Childhood Obesity Intervention Cost-Effectiveness Study (CHOICES) Learning Collaborative Partnership. This brief is intended for educational use only. Funded by The JPB Foundation. Results are those of the authors and not the funders.

← Back to Resources

Report: Utah: Sugary Drink Tax

Sugary drinks

The information in this report is intended to provide educational information on the cost-effectiveness of sugary drink excise taxes.

Executive Summary

Continually rising rates of obesity represent one of the greatest public health threats facing the United States. Obesity has been linked to excess consumption of sugary drinks. Federal, state, and local governments have considered implementing excise taxes on sugary drinks to reduce consumption, reduce obesity, and provide a new source of government revenue.1-4

We modeled implementation of a state excise tax on sugary drinks, at a tax rate of $0.02/ounce. Powdered drink mixes were modeled at a tax rate of $0.0025 per reconstituted fluid ounce according to the package instructions.

The tax modeled is projected to be cost-saving and result in lower levels of sugary drink consumption, thousands of cases of obesity prevented, and hundreds of millions of dollars in health care cost savings. For every dollar invested, this tax is projected to save $28.88 in health care costs.

Background 

Although sugary drink consumption has declined in recent years, adolescents and young adults in the United States consume more sugar than the Dietary Guidelines for Americans 2015-2020 recommends, with persistent racial and ethnic disparities.5-9 According to recent estimates, 27% of adults and 14% of youth in Utah drink at least one soda or other sugary drink per day.10,11 Public health researchers have suggested that excess intake of sugary drinks may be one of the single largest drivers of the obesity epidemic in the U.S.12 An estimated 26% of adults13 and 10% of youth14 in Utah have obesity.

Consumption of sugary drinks increases the risk of chronic diseases through changes in body mass index (BMI), insulin regulation, and other metabolic processes.15-17 Randomized intervention trials and longitudinal studies have linked increases in sugary drink consumption to excess weight gain, diabetes, cardiovascular disease, and other health risks.15-16 There are persistent racial and ethnic disparities across both sugary drink consumption levels and rates of obesity and chronic disease.5-8 In light of this evidence, the Dietary Guidelines for Americans 2015-20209 recommends that individuals limit sugary drink intake in order to manage their body weight and reduce their risk of chronic disease.

Targeted taxation has emerged as one recommended strategy to reduce consumption of sugary drinks.18 This strategy has been studied by public health experts, who have drawn on the success of tobacco taxation and decades of economic research to model the estimated financial and health impact of a sugary drink excise tax.19-22 Sugary drinks include all drinks with added caloric sweeteners. Proposed and enacted sugary drink excise taxes typically do not apply to 100% juice, milk products, or diet drinks. This report aims to model the projected effect of a sugary drink excise tax on projected health and disease outcomes over the next decade.

Modeling Framework: How excise taxes can lead to better health

State excise tax is linked to change in BMI through change in sugary drink price and consumption

Logic Model for Sugar Sweetened Beverage Tax


Key Terms
  • Excise tax: a consumption tax collected from retailers or distributors; it is reflected in the posted price (a sales tax in contrast is applied after purchase of the item)
  • Pass-through rate: how much of the excise tax on distributors is passed on to consumers as an increase in shelf price; a percent ranging from 0% (none of the tax) to 100% (all the tax)
  • Price elasticity of demand: how much consumer purchasing behavior changes following a change in price of an item
How does an excise tax work?

An infographic displaying the connection between tax, price, and demand.

How does an excise tax on distributors affect the price paid by consumers?

The first portion of the logical model above, highlighting excise tax and drink price.Since the cost of a sugary drink excise tax is incorporated directly into the beverage’s sticker price, an excise tax will likely influence consumer purchasing decisions more than a comparable sales tax that is added onto the item at the register. We assume 100% pass-through of the tax over 10 years and assume the tax rate would be adjusted annually for inflation. Our pass-through rate estimate is supported by empirical studies of excise taxes in Mexico and France that demonstrate near-complete pass-through rates to consumers.23 Short term studies for the local tax in Berkeley, CA indicate imperfect (or less than 100%) pass-through.3,24,25 More recent analyses from Philadelphia, PA indicate that over all the sales studied, pass-through was close to complete. The pass-through seen in pharmacies was higher than in supermarkets and mass merchandise settings.26 The expected change in sugary drink price was estimated using an average of $0.06/ounce based on national sugary drink prices.27 The price per ounce in this study was based on a weighted average of sugary drink consumption across stores, restaurants, and other sources according to the estimates from the National Health and Nutrition Examination Survey (NHANES) 2009-2010. The price per ounce of sugary drinks purchased in stores was calculated using weighted averages of two-liter bottles, 12-can cases, and single-serve containers based on 2010 Nielsen Homescan data.27 For example, a $0.02/ounce tax would raise the price of a 12-ounce can of soda from $0.72 to $0.96/can post-tax.

The middle portion of the Logic Model above, highlighting drink price and and drink consumption.How does increasing the price of sugary drinks change individual sugary drink consumption?

We used national estimates of sugary drink consumption from NHANES 2011-2016 adjusted to local race- and ethnicity-specific estimates of adult sugary drink consumption from the Utah Behavioral Risk Factor Surveillance System28 and youth sugary drink consumption from the Youth Behavioral Risk Surveillance System10 to estimate current sugary drink consumption levels in Utah. The mean own-price elasticity of demand for sugar-sweetened soft drinks (not including diet) is -1.21.29 The own-price elasticity reflects how much consumers will change their purchases in response to price changes. For example, an elasticity of -1.21 estimates that a 16% price increase would lead to a 19% reduction in purchases. Recent research on the Berkeley, CA tax found a 21% reduction in sugary drink intake among low-income populations consistent with this estimate.24

The final part of the Logic Model, highlighting drink consumption and BMI.

What are the individual health effects of decreasing sugary drink consumption?

Research has shown that decreasing sugary drink consumption can have positive effects on health in adults and youth. We conducted evidence reviews for the impact of a change in sugary drink intake on BMI, accounting for dietary compensation.22 Four large, multi-year longitudinal studies in adults16,30-32 were identified. The relationship was modeled using a uniform distribution based on the range of estimated effects on BMI due to reducing sugary drink intake; a one-serving reduction was associated with a BMI decrease of 0.21 kg/m2 to 0.57 kg/m2 in adults over a 3-year period. Among youth, a double-blind randomized controlled trial conducted over 18 months found that an additional 8-ounce serving of sugary drinks led to a 2.2 pound greater weight gain.33

Reach

The intervention applies to all youth and adults in Utah. However, the model estimates the health effects on those 2 years of age and older.*

*BMI z-scores were used in our analyses, which are not defined for children under 2 years of age.

Implementation Costs

We assume the tax will incur start-up and ongoing labor costs for tax administrators in the Utah State Tax Commission.34 To implement the intervention, the Utah State Tax Commission would need to process tax statements and conduct audits. Businesses would also need to prepare tax statements and participate in audits, which would require labor from private tax accountants. Cost information was drawn from localities with planned or implemented excise taxes on sugary drinks.22 The cost and benefit estimates do not include expected tax revenue.

CHOICES Microsimulation Model

The CHOICES microsimulation model for Utah was used to calculate the costs and effectiveness over 10 years (2017–27). Cases of obesity prevented were calculated at the end of the model period in 2027. The model was based on prior CHOICES work,22,35-37 and created a virtual population of Utah residents using data from: U.S. Census, American Community Survey, Behavioral Risk Factor Surveillance System, NHANES, National Survey of Children’s Health,37 the Medical Expenditure Panel Survey, multiple national longitudinal studies, and obesity prevalence data provided by Utah Department of Health. Using peer-reviewed methodology, we forecasted what would happen to this virtual population with and without a sugary drink tax to model changes in disease and mortality rates, and health care costs due to the tax.

An infographic outline the study's basic methodology.


Results: $0.02/ounce State Excise Tax on Sugary Drinks

Overall, the model shows that a sugary drink excise tax is cost-saving. Compared to the simulated natural history without a tax, the tax is projected to result in lower levels of sugary drink consumption, fewer cases of obesity, fewer deaths, and $132 million dollars in health care savings over the 10-year period under consideration.

The estimated reduction in obesity attributable to the tax leads to lower projected health care costs, offsetting tax implementation costs and resulting in net cost savings. The difference between total health care costs with no intervention and lower health care costs with an intervention represents health care costs saved; these savings can be compared to the cost of implementing the tax to arrive at the metric of health care costs saved per $1 invested.

The CHOICES microsimulation model does not include annual revenue generation from a state excise tax on sugary drinks in any of the cost-effectiveness calculations. Revenue is likely substantial. The Rudd Center Revenue Calculator for Sugary Drink Taxes estimates potential annual revenues from excise taxes on sugary drinks only and is “intended to provide a rough estimate” for municipalities to consider.38 According to the Rudd Center,38 a $0.02/ounce excise tax in Utah could raise as much as $181 million in 2019. Actual tax revenue may be lower than these projected estimates; the Rudd Center advises to adjust the revenues down by 10-30% to account for non-compliance. These would result in annual revenues of $127 – $163 million.

An infographic outlining the results of the 2 cent excise tax on sugary drinks.


Outcome $0.02/ounce excise tax
Mean
(95% uncertainty interval)
10 Year Reach* 3,430000
(3,420,000; 3,440,000)
First Year Reach* 2,950,000
(2,940,000; 2,940,000)
Decrease in 12-oz Servings of Sugary Drinks per Person in the First Year* 90
(55; 159)
Mean Reduction in BMI Units per Person* -0.176
(-0.330; -0.090)
10 Year Intervention Implementation Cost per Person $1.33
($1.30; $1.36)
Total Intervention Implementation Cost Over 10 Years $4.56 million
($4.48 million; $4.65 million)
Annual Intervention Implementation Cost $456,000
($448,000; $465,000)
Health Care Costs Saved Over 10 Years $132 million
($59.6 million; $271 million)
Net Costs Difference Over 10 Years -$127 million
(-$267 million; -$55.1 million)
Quality Adjusted Life Years (QALYs) Gained Over 10 Years 5,410
(2,470; 11,200)
Years of Life Gained Over 10 Years 1,190
(473; 2,750)
Deaths Prevented Over 10 Years* 354
(141; 791)
Years with Obesity Prevented Over 10 Years 137,000
(69,700; 259,000)
Health Care Costs Saved per $1 Invested Over 10 Years $28.88
($13.07; $58.76)
Cases of Obesity Prevented in 2027* 19,600
(9,900; 36,700)
Cases of Childhood Obesity Prevented in 2027* 2,670
(1,110; 6,150)
Cost per Year with Obesity Prevented Over 10 Years Cost-saving
Cost per QALY Gained Over 10 Years Cost-saving
Cost per YL Gained Over 10 Years Cost-saving
Cost per Death Averted Over 10 Years Cost-saving

Uncertainty intervals are estimated by running the model 1,000 times, taking into account both uncertainty from data sources and virtual population projections, and calculating a central range in which 95% of the model results fell.

All metrics reported for the population over a 10-year period and discounted at 3% per year, unless otherwise noted.

*Not discounted.

Results: $0.02/ounce State Excise Tax on Sugary Drinks by Race and Ethnicity

Outcome White, Non-Hispanic
Mean
(95% uncertainty interval)
Other, Non-Hispanic 
Mean
(95% uncertainty interval)
Hispanic
Mean
(95% uncertainty interval)
Decrease in 12-oz Serving of Sugary Drinks per Person in the First Year* 85
(52; 151)
89
(55; 156)
119
(73; 209)
Reduction in Obesity Prevalence in 2027* 1.00** 1.02
(0.87; 1.22)
1.74
(1.52; 1.99)
Health Care Costs Saved Over 10 Years $98.1 million
($44.6; $201 million)
$7.46 million
($3.37; $15.6 million)
$26.3 million
($11.9; $54.9 million)
QALYS Gained Over 10 Years 4,030
(1,830; 8,330)
324
(146; 682)
1,060
(491; 2,180)
Years of Life Gained Over 10 Years 963
(371; 2,200)
69
(11; 170)
163
(50; 384)
Years with Obesity Prevented Over 10 Years 96,100
(48,600; 180,000)
9,410
(4,770; 17,700)
31,500
(15,900; 58,900)
Cases of Obesity Prevented in 2027* 13,800
(6,890; 25,900)
1,320
(675; 2,520)
4,430
(2,180; 8,300)
Cases of Childhood Obesity Prevented in 2027* 1,690
(686; 3,780)
298
(119; 691)
765
(297; 1,740)

Uncertainty intervals are estimated by running the model 1,000 times, taking into account both uncertainty from data sources and virtual population projections, and calculating a central range in which 95 percent of the model results fell.

All metrics reported for the population over a 10-year period and discounted at 3% per year, unless otherwise noted.

*Not discounted.

*Reference category.

Pre-tax Sugary Drink Consumption in Utah by Race and EthnicityA bar graphing showing the Pre-tax Sugary Drink Consumption in Utah by Race and Ethnicity. White, Non-hispanic averages 7.7 ounces. Other, Non-Hispanic averages 8.0 ounces. Hispanic averages 10.7 ounces. The overall average is 8.1 ounces.

Pre-tax Obesity Prevalence in Utah by Race and Ethnicity

A bar graph of the Pre-tax Obesity Prevalence in Utah by Race and Ethnicity. White, Non-Hispanic shows 28.5%. Other, Non-White Hispanic shows 26.0%. Hispanic shows 33.3%. The overall average shows 28.9%.

Cases of Obesity Prevented in Utah in 2027*A graph showing the Cases of Obesity Prevented in Utah in 2027 if the 2 cent excise tax is implemented. Of the cases of obseity prevented in 2027 in Utah, 30% qualify as Other, including Hispanic. The Other, including Hispanic group comprises 21% of the total Utah population.

Decrease in Sugary Drink Consumption by Race and Ethnicity*A graph of the decrease in sugary drink consumption after the 2 cent excise tax. Each serving is considered 12 ounces. White, Non-Hispanic shows a decrease of 85 servings. Other, Non-Hispanic shows a decrease of 89 servings. Hispanic shows a decrease of 119 servings.

Impact on Diabetes

We estimated the impact of the tax-induced reduction in sugary drink intake on diabetes incidence for adults ages 18-79 years using a published meta-analysis of the relative risk of developing diabetes due to a one-serving change in sugary drink consumption39 as well as local estimates of diabetes. On average, each 8.5-ounce serving of sugary drinks per day increases the risk of diabetes by 18%.39
An infographic about diabetes prevention and dental health results after the 2 cent excise tax.

In Utah, we estimated that the proposed sugary drink excise tax would lead to a 7% reduction in diabetes incidence in the sugary drink tax model. Impact on diabetes incidence was calculated over one year once the tax reaches its full effect. Impact on diabetes was calculated based on summary results from the model, not directly via microsimulation.

Impact on Tooth Decay

We estimated the impact of a sugary drink excise tax on tooth decay cost using a longitudinal analysis of the relationship between intake of sugars and tooth decay in adults. On average, for every 10 grams higher intake of sugar per day, there is an increase in decayed, missing and filled teeth (DMFT) of approximately 0.10 over 10 years.40 As described above, we assume that the excise tax will result in a reduction in sugary drink intake. There are many studies showing a similar relationship between higher intake of sugars and tooth decay in children and youth41 and thus we assume the same relationship as found in adults.

We used the Bureau of Coverage and Reimbursement Policy Coverage and Reimbursement Fee Schedule42 data to estimate a Medicaid cost of treating DMFT as: $307.90 for a permanent crown and $45.54 for a filling. These codes reflect treatment for one surface and do not reflect higher reimbursement rates for multi-surface treatment, temporary crowns, or potential flat tax schedules. Based on analysis of data on tooth decay, fillings and crowns for the U.S. population from NHANES 1988-1994 (the last year crowns and fillings were separately reported),43 we estimate that 78.9% of tooth decay in children and 43.5% of tooth decay in adults is treated. Using this same data set, we estimate that 97% of treatment for children is fillings and 82.5% of treatment for adults is fillings.

To estimate Medicaid-specific dental caries cost savings, we used local estimates of the number of people enrolled in Medicaid and the proportion of people receiving Medicaid dental services. Because of limited Medicaid dental coverage for adults in Utah, only children are included in the Medicaid-specific calculations. In Utah, we estimated that a $0.02/ounce tax would lead to a total of $464,000 in Medicaid savings over a period of 10 years due to a reduction in treatment of DFMT. The Medicaid reimbursement tax estimates may underestimate the total cost savings of tooth decay treatment projected here as dental providers may charge higher amounts to patients.

Considerations for Health Equity

An infographic about individual and household savings on sugary drinks after the excise tax..Concerns have been raised regarding the impact of the tax on low-income households. For many goods, including cigarettes, low-income households are more price-sensitive than high-income peers. If this is also true for low-income sugary drink consumers, these households would spend less on sugary drinks after the tax goes into effect, which would free up disposable income for other consumer purchases.44 Using sales data from the Rudd Center Revenue Calculator for Sugary Drink Taxes,38 we project that individuals and households in Utah will spend less money on sugary drinks after the tax is implemented.

In addition, low-income consumers, on average, consume more sugary drinks than higher-income consumers. We project that greater health benefits from this policy will accrue to low-income consumers. We also project that greater health benefits will accrue among Hispanic Utah residents compared with non-Hispanic residents of white or other race. Using data from NHANES and Utah on sugary drink consumption in the CHOICES model, the average daily consumption of sugary drinks by people in Utah varies by race and ethnic group (see pre-tax graphs above). Under the proposed tax, Hispanic Utahns will experience a 74% greater reduction in obesity prevalence compared to White non-Hispanic residents. On that basis, the proposed tax could decrease disparities in obesity outcomes.

Implementation Considerations

Revenue raised from a sugary drink tax could also be reinvested in low-income communities. For instance, in Berkeley, CA, sugary drink tax revenue has been allocated for spending on school and community programs to promote healthy eating, diabetes, and obesity prevention; many serve low-income or minority populations.45,46 Public support for such taxes generally increases with earmarking for preventive health activities.46

There is opposition from the food and beverage industry, which spends billions of dollars promoting their products.47 Relatively small beverage excise taxes are currently applied across many states. The proposed tax is likely to be sustainable if implemented based on the successful history of tobacco excise taxes. There is potential for a shift in social norms of sugary drink consumption based on evidence from tobacco control tax and regulatory efforts.48 This shift in norms can be facilitated by taxing sugary drinks, which reduces the attractiveness of non-caloric drink options and discourages consumers from selecting any sugary drink options when making beverage decisions.

Conclusion

We project that implementation of a state excise tax on sugary drinks only, at a tax rate of $0.02/ounce, will prevent thousands of cases of childhood and adult obesity, prevent new cases of diabetes, increase healthy life years, and save more in future health care costs than it will cost to implement. Implementing the tax could also serve as a powerful social signal to reduce sugar consumption.

Suggested Citation:
McKinnon A, Ward ZJ, Barrett JL, Cradock AL, Resch SC, Flax CN, and Gortmaker SL. Utah: Sugary Drink Tax. The Salt Lake County Health Department and the CHOICES Learning Collaborative Partnership at the Harvard T.H. Chan School of Public Health, Boston, MA; December 2019.

The design for this report and its graphics were developed by Molly Garrone, MA and partners at Burness.

This work is supported by The JPB Foundation. This report is intended for educational use only. Results are those of the authors and not the funders.

Appendices

Appendices A and B showing the health effects of a $0.02/ounce excise tax on sugary drinks in Salt Lake County, UT, may be viewed starting on page 15 in the full report PDF.

← Back to Resources

References

  1. American Public Health Association Taxes on Sugar-Sweetened Beverages. 2012.
  2. Hakim D, Confessore N. Paterson seeks huge cuts and $1 billion in taxes and fees. New York Times. January 19, 2010.
  3. Falbe J, Rojas N, Grummon AH, Madsen KA. Higher Retail Prices of Sugar-Sweetened Beverages 3 Months After Implementation of an Excise Tax in Berkeley, California. American Journal of Public Health. 2015;105(11):2194-2201.
  4. Leonhardt D. The battle over taxing soda. The New York Times. May 19, 2010.
  5. Wang YC, Bleich SN, Gortmaker SL. Increasing caloric contribution from sugar-sweetened beverages and 100% fruit juices among US children and adolescents, 1988-2004. Pediatrics. 2008;121(6):E1604-E1614.
  6. Bleich SN, Wang YC, Wang Y, Gortmaker SL. Increasing consumption of sugar-sweetened beverages among US adults: 1988-1994 to 1999-2004. American Journal of Clinical Nutrition. 2009;89(1):372-381.
  7. Kit BK, Fakhouri THI, Park S, Nielsen SJ, Ogden CL. Trends in sugar-sweetened beverage consumption among youth and adults in the United States: 1999-2010. American Journal of Clinical Nutrition. 2013;98(1):180-188.
  8. Bleich SN, Vercammen KA, Koma JW, Li ZH. Trends in Beverage Consumption Among Children and Adults, 2003-2014. Obesity. 2018;26(2):432-441.
  9. U.S. Department of Health and Human Services, U.S. Department of Agriculture. 2015 – 2020 Dietary Guidelines for Americans. December 2015.
  10. Centers for Disease Control and Prevention (CDC), Utah Department of Health. Youth Risk Behavior Surveillance System. 2017.
  11. Park S, Xu F, Town M, Blanck H. Prevalence of Sugar-Sweetened Beverage Intake Among Adults – 23 States and the District of Columbia, 2013. MMWR Morb Mortal Wkly Report 2016. 2016;65(7):169-174.
  12. Brownell KD, Frieden TR. Ounces of Prevention – The Public Policy Case for Taxes on Sugared Beverages. New England Journal of Medicine. 2009;360(18):1805-1808.
  13. Utah Department of Health. (2018). Public Health Indicator Based Information System (IBIS) Utah’s Public Health Data Source. Health Indicator of Overweight or Obese. https://web.archive.org/web/20240602081345/https://ibis.health.utah.gov/ibisph-view/indicator/view/OvrwtObe.UT_US.html
  14. Utah Department of Health. (2018). Public Health Indicator Based Information System (IBIS) Utah’s Public Health Data Source. Health Indicator of Obese Among Children and Adolescents. https://web.archive.org/web/20240229044546/https://ibis.health.utah.gov/ibisph-view/indicator/view/OvrwtChild.LHD.html
  15. Malik VS, Pan A, Willett WC, Hu FB. Sugar-sweetened beverages and weight gain in children and adults: a systematic review and meta-analysis. American Journal of Clinical Nutrition. 2013;98(4):1084-1102.
  16. Chen L, Caballero B, Mitchell DC, et al. Reducing Consumption of Sugar-Sweetened Beverages Is Associated with Reduced Blood Pressure: A Prospective Study among U.S. Adults. Circulation. 2010;121(22):2398-2406.
  17. Wang Y. The potential impact of sugar-sweetened beverage taxes in New York State. A report to the New York State Health Commissioner. New York: Columbia Mailman School of Public Health. 2010.
  18. IOM (Institute of Medicine), National Research Council. Local Government Actions to Prevent Childhood Obesity. Washington, DC: The National Academies Press; 2009.
  19. Chaloupka F, Powell L, Chriqui J. Sugar-sweetened beverage taxes and public health: A Research Brief. Minneapolis, MN; 2009.
  20. Brownell KD, Farley T, Willett WC, et al. The Public Health and Economic Benefits of Taxing Sugar-Sweetened Beverages. New England Journal of Medicine. 2009;361(16):1599-1605.
  21. Long M, Gortmaker S, Ward Z, et al. Cost Effectiveness of a Sugar-Sweetened Beverage Excise Tax in the U.S. American Journal of Preventive Medicine. 2015;49(1):112-123.
  22. Gortmaker SL, Wang YC, Long MW, et al. Three Interventions That Reduce Childhood Obesity Are Projected To Save More Than They Cost To Implement. Health Affairs. 2015;34(11):1932-1939.
  23. Colchero MA, Salgado JC, Unar-Munguia M, Molina M, Ng SW, Rivera-Dommarco JA. Changes in Prices After an Excise Tax to Sweetened Sugar Beverages Was Implemented in Mexico: Evidence from Urban Areas. PLoS One. 2015;10(12):11.
  24. Falbe J, Thompson HR, Becker CM, Rojas N, McCulloch CE, Madsen KA. Impact of the Berkeley Excise Tax on Sugar-Sweetened Beverage Consumption. American Journal of Public Health. 2016;106(10):1865-1871.
  25. Ng S, Silver L, Ryan-Ibarra S, et al. Berkeley Evaluation of Soda Tax (BEST) Study Preliminary Findings. Presentation at the annual meeting of the American Public Health Association. Paper presented at: Presentation at the annual meeting of the American Public Health Association; November, 2015; Chicago, IL.
  26. Roberto CA, Lawman HG, LeVasseur MT, Mitra N, Peterhans A, Herring B, Bleich SN. Association of a Beverage Tax on Sugar-Sweetened and Artificially Sweetened Beverages With Changes in Beverage Prices and Sales at Chain Retailers in a Large Urban Setting. JAMA. 2019 May 14;321(18):1799-1810. doi: 10.1001/jama.2019.4249.
  27. Powell L, Isgor z, Rimkus L, Chaloupka F. Sugar-sweetened beverage prices: Estimates from a national sample of food outlets. Chicago, IL: Bridging the Gap Program, Health Policy Center, Institute for Health Research and Policy, University of Illinois at Chicago;2014.
  28. Centers for Disease Control and Prevention (CDC), Utah Department of Health. Utah Behavioral Risk Factor Surveillance System. 2013.
  29. Powell LM, Chriqui JF, Khan T, Wada R, Chaloupka FJ. Assessing the Potential Effectiveness of Food and Beverage Taxes and Subsidies for Improving Public Health: A Systematic Review of Prices, Demand and Body Weight Outcomes. Obesity reviews: an official journal of the International Association for the Study of Obesity. 2013;14(2):110-128.
  30. Mozaffarian D, Hao T, Rimm EB, Willett WC, Hu FB. Changes in Diet and Lifestyle and Long-Term Weight Gain in Women and Men. New England Journal of Medicine. 2011;364(25):2392-2404.
  31. Palmer JR, Boggs DA, Krishnan S, Hu FB, Singer M, Rosenberg L. Sugar-Sweetened Beverages and Incidence of Type 2 Diabetes Mellitus in African American Women. Archives of Internal Medicine. 2008;168(14):1487-1492.
  32. Schulze MB, Manson JE, Ludwig DS, et al. Sugar-sweetened beverages, weight gain, and incidence of type 2 diabetes in young and middle-aged women. JAMA-J Am Med Assoc. 2004;292(8):927-934.
  33. de Ruyter JC, Olthof MR, Seidell JC, Katan MB. A trial of sugar-free or sugar-sweetened beverages and body weight in children. New England Journal of Medicine. 2012;367(15):1397-1406.
  34. Personal Communication with Utah State Tax Commission. 2019.
  35. Ward ZJ, Long MW, Resch SC, Giles CM, Cradock AL, Gortmaker SL. Simulation of Growth Trajectories of Childhood Obesity into Adulthood. New England Journal of Medicine. 2017;377(22):2145-2153.
  36. Ward ZJ, Long MW, Resch SC, et al. Redrawing the US Obesity Landscape: Bias-Corrected Estimates of State-Specific Adult Obesity Prevalence. PLoS One. 2016;11(3):13.
  37. Long MW, Ward Z, Resch SC, et al. State-level estimates of childhood obesity prevalence in the United States corrected for report bias. International Journal of Obesity. 2016;40(10):1523-1528.

  38. UCONN Rudd Center. Revenue Calculator for Sugary Drink Taxes. 2014; https://uconnruddcenter.org/tax-calculator/. Accessed November, 2019.
  39. Imamura F, O’Connor L, Ye Z, et al. Consumption of sugar sweetened beverages, artificially sweetened beverages, and fruit juice and incidence of type 2 diabetes: systematic review, meta-analysis, and estimation of population attributable fraction. Br J Sports Med. 2016;50(8):496-U484.
  40. Bernabe E, Vehkalahti MM, Sheiham A, Lundqvist A, Suominen AL. The Shape of the Dose-Response Relationship between Sugars and Caries in Adults. Journal of Dental Research. 2016;95(2):167-172.
  41. Sheiham A, James WPT. A new understanding of the relationship between sugars, dental caries and fluoride use: implications for limits on sugars consumption. Public Health Nutrition. 2014;17(10):2176-2184.
  42. Utah Department of Health Medicaid. Bureau of Coverage and Reimbursement Policy Coverage and Reimbursement Fee Schedule Download. 2019.
  43. Ward Z, et al. NHANES III Dental Examination: An Incisive Report. unpublished report; 2018.
  44. Farrelly MC, Bray JW. Response to increases in cigarette prices by race/ethnicity, income, and age groups – United States, 1976-1993 (Reprinted from MMWR, vol 47, pg 605-609, 1998). JAMA-J Am Med Assoc. 1998;280(23):1979-1980.
  45. Lynn J. City Council votes to allocate ‘soda tax’ revenue to school district, city organizations. The Daily Californian. Jan. 20, 2016, 2016.
  46. Berkeley City Council. (2016, June 14). Berkeley City Council meeting. [Annotated Agenda]. Retrieved from https://berkeleyca.gov/.
  47. Federal Trade Commission. A review of food marketing to children and adolescents: follow-up report. Washington, DC Dec 2012 2012.
  48. Frieden TR, Mostashari F, Kerker BD, Miller N, Hajat A, Frankel M. Adult tobacco use levels after intensive tobacco control measures: New York City, 2002-2003. American Journal of Public Health. 2005;95(6):1016-1023


Brief: Active Recess in Salt Lake County, Utah

Three kids at the playground

The information in this brief is intended only to provide educational information.

The following provides a summary of findings from the CHOICES Learning Collaborative Partnership simulation model of an Active Recess policy in schools in Salt Lake County, UT to increase students’ physical activity levels during recess by installing playground markings, providing portable play equipment, and/or providing adult-led engaging activity options.

The Issue

Over the past three decades, obesity has nearly tripled in Utah.1 In the United States, health care costs for treating obesity-related health conditions such as heart disease and diabetes were $147 billion in 2008.2 Emerging prevention strategies directed at children show great promise for addressing this issue.3 Evidence shows that physical activity helps kids grow up at a healthy weight.

In Utah, only 19% of children meet the recommended 60 minutes of daily physical activity.4 Among all counties in Utah, Salt Lake County has the second highest rate of children with obesity.5 Recess periods during the school day typically last 10-15 minutes or more and are scheduled as isolated breaks or in association with lunch.6,7 Elementary school children generally spend more time in recess than physical education weekly.8 Schools often lack resources that can encourage physical activity during recess such as supportive supervision, play facilities, and equipment.9,10 On average, children spend less than 50% of recess time engaged in moderate-to-vigorous physical activity (MVPA).10

About Active Recess

We assumed that implementation would occur district-wide in public elementary and charter schools in the four school districts in Salt Lake County that provide recess but do not currently require the use of Active Recess strategies. Future grant funding would provide for installation of playground markings, provision of portable play equipment, and/or provision of adult-led engaging activities designed to increase students’ physical activity levels during school recess time. Playground markings would be installed for adult-led games that engage children in physical activity (e.g., four square, hop-scotch) and participating schools would receive portable playground equipment for use during recess time.

Comparing Costs and Outcomes

CHOICES cost-effectiveness analysis compared the costs and outcomes of implementing an Active Recess policy over 10 years (2017-2027) to costs and outcomes if the policy is not implemented. The approach assumes that no school is currently implementing Active Recess practices in these four districts, and 94% of these schools adopt Active Recess practices where all students benefit.

Implementing Active Recess is an investment in the future. By the end of 2027:
A stylized list featuring the following information: 196,00 children reached; 141 cases of childhood obesity prevented; 4% increase in MVPA.

Conclusions and Implications

Every child deserves a healthy start in life. An Active Recess policy in Salt Lake County could help ensure that more kids have opportunities to be physically active during recess, no matter which school district they are in. Implementing a district-level policy in these Salt Lake County public elementary schools and charter schools would require an investment of $24 per student to provide the equipment and resources needed to increase physical activity levels during recess.

These results reinforce the importance of investing in prevention efforts to reduce the prevalence of obesity. This intervention would prevent 141 cases of childhood obesity in 2027 and provide the opportunity for 196,000 children to engage in active recess opportunities. For every $1.00 spent on implementing the Active Recess policy, $0.06 in health care costs would be saved. While not quantified in this analysis, there are also other positive benefits from physical activity related to cognition and academic performance that may also result in additional cost savings.11

Evidence is growing about how to help children grow up at a healthy weight. Strategies such as Active Recess are laying the foundation for a healthier future by helping schools create environments that nurture healthy habits.

References

  1. Utah Department of Health. (2018). Public Health Indicator Based Information System (IBIS) Utah’s Public Health Data Resource, Health Indicator Report of Overweight or Obese. https://ibis.health.utah.gov/ibisph-view/indicator/view/OvrwtObe.UT_US.html
  2. Finkelstein EA, Trogdon JG, Cohen JW, Dietz W. Annual Medical Spending Attributable To Obesity: Payer-And Service-Specific Estimates. Health Affairs. 2009;28(5).
  3. Gortmaker SL, Wang YC, Long MW, et al. Three Interventions That Reduce Childhood Obesity are Projected to Save More Than They Cost to Implement. Health Affairs, 2015, 34(11), 1932–193
  4. Utah Department of Health. (2018). Public Health Indicator Based Information System (IBIS) Utah’s Public Health Data Resource, Health Indicator Report of Physical Activity Among Adolesents. https://ibis.health.utah.gov/ibisph-view/indicator/view/PhysActAdol.UT_US.html
  5. Utah Department of Health. (2018). Public Health Indicator Based Information System (IBIS) Utah’s Public Health Data Resource, Health Indicator Report of Obesity Among Children and Adolescents. https://ibis.health.utah.gov/ibisph-view/indicator/view/OvrwtChild.LHD.html
  6. Parsad B & Lewis L. Calories In, Calories Out: Food and Exercise in Public Elementary Schools, 2005, National Center for Education Statistics, U.S. Department of Education Report No. NCES 2006–057, (2006). https://nces.ed.gov/pubs2006/2006057.pdf. Accessed January 24, 2017.
  7. Centers for Disease Control and Prevention. The Association Between School-Based Physical Activity, Including Physical Education, and Academic Performance. Atlanta, GA: U.S. Department of Health and Human Services; (2010). https://www.cdc.gov/ healthyyouth/health_and_academics/pdf/pa-pe_paper.pdf. Accessed January 24, 2017.
  8. Robert Wood Johnson Foundation. Recess Rules: Why the Undervalued Playtime May Be America’s Best Investment for Healthy Kids and Healthy Schools. Princetown, NJ: Robert Wood Johnson Foundation; 2007.
  9. National Association for Sport and Physical Education. Recess for Elementary School Students: A Position Paper, Council on Physical Education for Children Report, (2006). http://files.eric.ed.gov/fulltext/ED497155.pdf. Accessed January 24, 2017.
  10. Stratton G. Promoting Children’s Physical Activity in Primary School: An Intervention Study Using Playground Markings. Ergonomics, 2000, 43(10), 538-1546.
  11. 2018 Physical Activity Guidelines Advisory Committee. 2018 Physical Activity Guidelines Advisory Committee Scientific Report. Washington, DC: U.S. Department of Health and Human Services, 2018. Accessed September 7, 2018
Suggested Citation:

McKinnon A, Barrett JL, Cradock AL, Flax CN. Salt Lake County: Active Recess {Issue Brief}. Salt Lake County Health Department, Salt Lake City, UT, and the CHOICES Learning Collaborative Partnership at the Harvard T.H. Chan School of Public Health, Boston, MA; December 2019.

The design for this brief and its graphics were developed by Molly Garrone, MA and partners at Burness.

This issue brief was developed at the Harvard T.H. Chan School of Public Health in collaboration with the Salt Lake County Health Department through participation in the Childhood Obesity Intervention Cost-Effectiveness Study (CHOICES) Learning Collaborative Partnership. This brief is intended for educational use only. Funded by The JPB Foundation. Results are those of the authors and not the funders.

← Back to Resources

Brief: Best Practice Guidelines for Healthy Childcare in Detroit

The information in this brief is intended only to provide educational information.

This brief summarizes a CHOICES Learning Collaborative Partnership model for Best Practice Guidelines for Healthy Childcare in Detroit, MI. We assume a proportion of licensed programs would voluntarily adopt guidelines to eliminate sugary drinks and limit screen time. Participation rates are based on the number of programs voluntarily achieving 3+ star ratings from Great Start to Quality Program.1

The Issue

All children deserve the opportunity to be healthy. However, if current trends in childhood obesity continue, most of today’s children will have obesity at age 35.2 The health impacts and health care costs of treating obesity-related conditions in adulthood, such as heart disease and diabetes, cost $147 billion in 2008.3 However, research shows that avoiding sugary drinks and viewing less TV can help kids grow up at a healthy weight.

Early childcare programs are essential partners in supporting healthy habit development. Approximately 11,000 2-5 year-olds attend licensed childcare centers and family homes in Detroit.4 Providing training and technical assistance on guidelines to eliminate sugary drinks and limit non-educational screen time to 30 minutes per week would positively impact the children attending licensed childcare programs.

About the Best Practice Guidelines for Healthy Childcare Model

Best Practice Guidelines for Healthy Childcare would be put forth by the Detroit Health Department. The United Way provides professional development for early childcare professionals and would offer new voluntary training and technical assistance opportunities to early childcare providers. In turn, providers would implement the guidelines in their programs. The guidelines would encourage early childcare programs to not serve sugary drinks and to reduce non-educational television time to 30 minutes per week during program time. We estimate that 62% of centers and 30% of family childcare homes would voluntarily adopt the guidelines.1

Comparing Costs and Outcomes

CHOICES cost-effectiveness analysis compared the costs and outcomes over a 10-year time horizon (2017-2027) of implementing Best Practice Guidelines for Healthy Childcare vs. not implementing the guidelines.

Implementing Best Practice Guidelines for Healthy Childcare is an investment in the future and would save early childcare programs money. By the end of 2027, the model projects:
over 19,000 children will be healthier, 43 cases of childhood obesity prevented, $1,150 saved per childcare center, $195 saved per family childcare home

Conclusions and Implications

Every child deserves a healthy start in life. This includes ensuring that all children in childcare have less exposure to beverages with added sugar and no nutritional value and have less exposure to screen time. Implementing Best Practice Guidelines for Healthy Childcare has the potential to reach 19,400 children ages 2-5 years in licensed childcare programs in Detroit. These children would consume fewer beverages with added sugar and view less screen time. In particular, children in family childcare homes would watch 2.3 fewer hours of screen time daily if the guidelines are met. This intervention would cost $107,000 to implement, though childcare program providers would save money when they are no longer serving sugary drinks. Overall, the CHOICES model estimates that there is a 97% chance that the intervention would be cost-saving. That is, it could save more due to the reduction in spending associated with serving sugary beverages than it may cost to implement.

The first few years of childhood can be an important time to promote healthy lifestyle behaviors. Implementing Best Practice Guidelines for Healthy Childcare could lay the foundation by ensuring that all children in childcare settings drink beverages that promote their health and have less exposure to screen time.

References

  1. Great Start to Quality Participation Data, July 1 2019. https://web.archive.org/web/20210813041905/https://greatstarttoquality.org/great-start-quality-participation-data Accessed July 17 2019.
  2. Ward Z, Long M, Resch S, Giles C, Cradock A, Gortmaker S. Simulation of Growth Trajectories of Childhood Obesity into Adulthood. New England Journal of Medicine. 2017 Nov 30;377(22):2145-2153.
  3. Finkelstein EA, Trogdon JG, Cohen JW, Dietz W. Annual Medical Spending Attributable To Obesity: Payer-And Service-Specific Estimates. Health Affairs. 2009;28(5).
  4. Per previous estimates that 79% of children in day care are ages 2-5 years old out of the 0-5 year old population
Suggested Citation:

Hill AB, Mozaffarian RS, Barrett JL, Cradock AL. Detroit: Best Practice Guidelines for Healthy Childcare [Issue Brief]. Detroit Health Department and United Way for Southeastern Michigan, Detroit, MI, and the CHOICES Learning Collaborative Partnership at the Harvard T.H. Chan School of Public Health, Boston, MA; December 2019.

The design for this brief and its graphics were developed by Molly Garrone, MA and partners at Burness.

This issue brief was developed at the Harvard T.H. Chan School of Public Health in collaboration with the Detroit Health Department through participation in the Childhood Obesity Intervention Cost-Effectiveness Study (CHOICES) Learning Collaborative Partnership. This brief is intended for educational use only. Funded by The JPB Foundation. Results are those of the authors and not the funders.

← Back to Resources

Brief: Active Physical Education (PE) in Hawaii

Young children playing outside during physical education class time

The information in this brief is intended only to provide educational information.

This brief summarizes the findings from a CHOICES Learning Collaborative Partnership simulation model of statewide implementation of the Hawaii State Department of Education (DOE) “Active PE” Wellness Guideline that requires 50% of physical education (PE) class be dedicated to moderate-to-vigorous physical activity (MVPA).

The Issue

Every child deserves the opportunity to be healthy. Research shows that physical activity helps kids grow up at a healthy weight and reduces risk of future chronic disease.1 If current trends continue in the United States, more than half of today’s children will have obesity at age 35.2 Health care costs for treating obesity-related health conditions such as heart disease and diabetes were $147 billion in 2008.3 The best chance we have to make sure kids grow up to be healthy is while they are still growing.

Although participation in physical education (PE) can help students meet the national recommendation of 60 minutes of physical activity per day,1 less than half of PE minutes are typically active.4 Hawaii DOE wellness guidelines say that elementary school students in DOE schools should receive at least 45 minutes of PE per week.5 The purpose of this study is to estimate the cost-effectiveness of implementing the Active PE guideline, which requires that at least 50% of PE time be spent in MVPA.

About Active PE

The hypothetical statewide implementation of the Active PE wellness guideline would include dissemination of the evidence-based program SPARK PE to elementary schools in Hawaii. SPARK is a widely used program that has been found to increase MVPA time in PE class.6

District PE Resource Teachers would receive professional development to become SPARK certified trainers, and then would train elementary PE teachers in subsequent years. All trained teachers would receive SPARK curricula and instructional materials, and all eligible schools would receive SPARK equipment. Implementation would include a state-level PE Educational Specialist to provide oversight and monitoring of policy implementation, as well as ongoing training and support for teachers and schools each year.

Comparing Costs and Outcomes

CHOICES cost-effectiveness analysis compared the costs and outcomes over a 10-year time horizon (2017-2027) of the statewide implementation of the Active PE wellness guideline with the costs and outcomes associated with not developing a comprehensive plan to fully implement the guideline. We assumed that all designated PE specialists, who are employed in 65% of schools, would be trained in SPARK. In schools without a PE specialist, one general classroom teacher per grade would be trained. Using this approach, 58% of students in grades K-6 would benefit from this intervention.

Implementing Active PE is an investment in the future. By the end of 2027:
If Active PE was implemented in Hawaii, 126,000 children would be reached. It would cost $4.67 million to implement Active PE over 10 years, at a cost of $37.10 per child.

Conclusions and Implications

The statewide implementation of the Active PE guideline, using the evidence-based program SPARK, is projected to have a widespread reach and positive impact, at an investment cost that appears reasonable compared to alternative approaches for increasing physical activity among children.7 The intervention would reach 126,000 children and would cost $37.10 per child to implement over 10 years. We project that Active PE implementation would increase MVPA by nearly 3 minutes per PE class for each child. We estimate there will be 19 fewer cases of childhood obesity in the final year of the model as a result of implementation of the Active PE guideline.

If Hawaii DOE schools were able to offer 150 minutes per week for elementary school students,8 we project the health benefits for children to be even higher. MVPA would increase by over 9 minutes per week per child and 65 cases of childhood obesity would be prevented in the final year of the model.

SPARK training offers a professional development opportunity for teachers to learn new instructional strategies to foster a fun and enjoyable environment where children can gain lifelong skills to engage in physical activity.9 There are likely positive benefits from physical activity related to improved bone health, aerobic and muscular fitness, cognition and academic performance1 that are not quantified in this analysis, but are important outcomes for children’s education and well-being.

While evidence is growing about how to help children achieve a healthy weight, there is currently not one single strategy that will reverse the obesity epidemic on its own. Active PE is one evidence-based strategy that can benefit the majority of students and can be incorporated into a comprehensive plan to address childhood obesity. Leaders at the state level should use the best available evidence to select strategies to help children be more active.

References

  1. 2018 Physical Activity Guidelines Advisory Committee. 2018 Physical Activity Guidelines Advisory Committee Scientific Report. Washington, DC: U.S. Department of Health and Human Services, 2018. Accessed September 7, 2018.
  2. Ward ZJ, Long MW, Resch S, Giles CM, Cradock AL, Gortmaker SL. Simulation of Growth Trajectories of Childhood Obesity into Adulthood. New England Journal of Medicine. 2017; 377(22): 2145-2153.
  3. Finkelstein EA, Trogdon JG, Cohen JW, Dietz W. Annual Medical Spending Attributable To Obesity: Payer-And Service-Specific Estimates. Health Affairs. 2009;28(5).
  4. Institute of Medicine. Educating the Student Body: Taking Physical Activity and Physical Education to School. Washington, DC: National Academies Press; 2013.
  5. Hawaii State Department of Education. Hawaii State Department of Education Wellness Guidelines. Retrieved from: http://www.hawaiipublicschools.org/DOE%20Forms/Health%20and%20Nutrition/Wellness-Guidelines-Implementation-Checklist.pdf. Accessed 12 April 2018.
  6. Sallis JF, McKenzie TL, Alcaraz JE, Kolody B, Faucette N, & Hovell MF. The effects of a 2-year physical education program (SPARK) on physical activity and fitness in elementary school students. Sports, Play and Active Recreation for Kids. American Journal of Public Health. 1997; 87(8), 1328-1334.
  7. Cradock AL, Barrett JL, Kenney EL, Giles CM, Ward ZJ, Long MW, … & Gortmaker SL. Using cost-effectiveness analysis to prioritize policy and programmatic approaches to physical activity promotion and obesity prevention in childhood. Preventive Medicine. 2017; 95, S17-S27.
  8. Society of Health and Physical Educators (SHAPE). Physical Education Guidelines. Retrieved from: https://www.shapeamerica.org/standards/guidelines/peguidelines.aspx. Accessed 13 April 2018.
  9. McKenzie TL, Sallis JK, & Rosengard P. Beyond the stucco tower: Design, development, and dissemination of the SPARK physical education programs. Quest. 2009;61(1), 114-127.
Suggested Citation:

Irvin L, Ryan J, Ching L, Starr R, Yamauchi J, La Chica T, Reiner JF, Barrett JL, Giles CM, Tao H, Gortmaker SL, Ward ZJ, Cradock AL. Hawaii: Active Physical Education (PE) {Issue Brief}. Hawaii Department of Public Health, Honolulu, HI, and the CHOICES Learning Collaborative Partnership at the Harvard T.H. Chan School of Public Health, Boston, MA; July 2019.

The design for this brief and its graphics were developed by Molly Garrone, MA and partners at Burness.

This issue brief was developed at the Harvard T.H. Chan School of Public Health in collaboration with the Hawaii Department of Health (MDH) through participation in the Childhood Obesity Intervention Cost-Effectiveness Study (CHOICES) Learning Collaborative Partnership. This brief is intended for educational use only. Funded by The JPB Foundation. Results are those of the authors and not the funders.

← Back to Resources